
Category: 1 PhD Ponderings

The category PhD Ponderings includes posts that I wrote while working through my PhD studies.

  • Navigating the Healthcare System

    Navigating the Healthcare System

    This post is a continuation on my discussion about Patient Health Literacy. The narrative that resulted from this study has been published on Amazon. See my Memoir page. The original source that I used for my study can be found at https://bcbecky.com.

    In reviewing the posts categorized as Navigating the healthcare system, I constructed the following themes: (1) learning processes, (2) taking control, (3) dealing with insurance, and (4) waiting. The theme learning processes applies to posts where I describe the different interactions I’m having with healthcare providers. The theme taking control applies to posts where I voice my need to empower myself or others by exerting some form of control over a situation. The theme dealing with insurance applies to posts where I write about issues insurance coverage of medication and treatments. The theme waiting applies to posts where I write about issues with waiting for various test results or treatments. I discuss each of these themes in more detail in the in the following sections.

    Learning Processes

    In the beginning I had no understanding of how the medical system worked with respect to cancer treatment. My understanding came only from what I saw on television and from an acquaintance that I sailed with 15 years ago who happened to be a medical oncologist. From that, I knew that there were different types of oncologist, but I did not understand that breast cancer treatment typically begins with surgery. Throughout the blog, I explore and share my interactions with the medical system, as I learn to negotiate it.

    In Canada, I likely would not have had much choice in where I received treatment. I also would not have thought that a I had any choice in surgeon or oncologist. I would go to who I was referred to. In the US, and specifically in the area where I live, there are multiple providers. In some ways insurance affects where you get treatment, but I had really good insurance that allowed me the option of choosing. After hearing the words ‘you have cancer’ I felt an immediate sense of lack of control. The ability to choose a healthcare provider, although stressful and a completely new process for me, was also a way to exert some control over the situation.

    As all the processes were new to me, I explained them in detail as they occurred. For example, in A long day (June 19, 2014), I explain the process of the appointment with the surgeon as well as the “whirs, honks, and other sounds” associated with my first experience with magnetic resonance imaging (MRI). I continue with the description of processes on my first day of chemotherapy, where I also include images that provide visual documentation of the process (First day of chemo, July 7, 2014). Further, in This too shall pass (July 16, 2014), I describe how:

    They don’t give you much other than anti-nausea meds for the first cycle, and they wait for you to call. The idea is that everyone experiences chemo differently, so they don’t know what you will need. They wait until they find out what you need then prescribe it. At this point, it is all about managing the symptoms. Unless the problem is life threatening (more life threatening than the cancer), the goal is to keep with the chemo regime on schedule through to the end.
    Images fromFirst day of chemo, July 7, 2014

    In addition to describing the medical process, I also described what I learned about the process of gathering information from my care team. In I had to give myself permission to nap (July 9, 2014), I outline what I learned about how nurses and physicians provide different levels of information:

    Nurses tend to provide advice on the extreme side of things. For example, absolutely no alcohol, no swimming, no biking. They tend to provide advice based upon the worst-case scenario, but also discount mental health. The need to exercise is important to my mental health. The oncologist is good – he explains the chemo cycle – and says it is OK to swim the first week, but as my white blood counts get low to stop swimming until the counts return.

    My analysis also shows that, in addition to describing the processes as I recalled them, I also wrote about my observations regarding medical education from the interpersonal perspective:

    What has been interesting is that this seems to be part of the learning process. Those who are most empathetic are the attending surgeons. The residents are still learning, so their interactions can feel a little mechanical – they are still trying to figure out the best ways to make connections with patients, but also the best ways to describe things. By the time they are fellows, you see a higher level of confidence in their ability to provide patient education – and you start to see information that is more customization to your specific case. The attending surgeons seem to be the best at tailoring their discussions to your specific situation.

    Finally, when I was hospitalized after surgery, I described my experience with hospital processes, specifically how a private room meant that my husband could stay the night with me, and the quality and process of getting food: “One thing that impressed me about the university hospital is that they use a room service model for food. The menu is quite good, and so far, the food has been good. The food is locally sourced where possible, and there are organic options” (An update from the hospital, November 20, 2014).

    Taking Control

    From the beginning I tried to take control by booking appointments for a second opinion from the university healthcare system. Here I was immediately frustrated at an inability to get an appointment without a confirmed pathology. Fortunately, they did guarantee me an appointment when the pathology results were confirmed (The speed of things, June 15, 2014). After getting an appointment, the act itself of seeking a second opinion and making a choice as to where to get healthcare were ways that I could take control (Double-mastectomy and chemo, June 19, 2014).

    When I began to experience some odd side effects, specifically blisters on my hands, that were not resolving, we made the decision to go to the emergency room. This was in part so that we could experience the process of the emergency room at a time when we were not overly stressed – that is, “while I was happily ambulatory and not ‘really sick’, just in case I needed the services at a later time” (Not without incident, July 13, 2014). Further, in Engaged patient in a hospital gown? (September 27, 2014), I describe the process of a typical doctors’ appointment – and how I take as much control as I can during those appointments, in this case by wearing a hoody over the hospital gown.

    Dealing with Insurance

    The role of insurance in the treatment for breast cancer both surprised and outraged me. I was surprised when one of the first things the surgeon told me, after telling me he recommended a double mastectomy, was the ‘good news’ that insurance was required to pay for reconstruction (How do you prepare to lose a body part?, June 15, 2014). I was surprised when the oncologist mentioned that “it also takes about a week to get approvals from the insurance company” (Caution – this one talks a bit about death, June 21, 2014) before I could start chemotherapy.

    We ran into issues with insurance and treatment after my first day of chemotherapy, which required the white blood cell booster Neulasta to be administered the following day. Insurance changed the way in which it was to be delivered (Pains with the American System, July 7, 2014). Finally, with a slightly more nuanced understanding of the way insurance impacts healthcare in the United States, I write a response to a New York Times article expressing my concern “that research stated like this gives insurance companies a reason not to pay for the surgery, when it may be in the best interest of the individual” (Bilateral mastectomies, July 28, 2014).

    Waiting

    Waiting was something that I ran into from the very beginning. First it was waiting for the pathology results, as I could not make an appointment at the university cancer center without confirmed pathology (The speed of things, June 16, 2013). When we were deciding on where to get treatment, we knew that we would be spending more time waiting at the university cancer center. We took waiting into consideration when making our decision, specifically I write:

    In the first couple weeks after diagnosis, I had decided where I was going to get treatment. I based this, in part, on where I felt comfortable – but also who provided me with the most options. I really liked being in a teaching setting and having access to more specialists – but that was balanced with knowing that I would spend more time in waiting rooms and receive less fancy care (e.g. the infusion treatment center doesn’t provide lunch).

    As I went through treatment, there were many occasions where I describe what I felt to be excessive wait times. For example, “It turned into a long day. We had a delay seeing the nurse practitioner to get sign off on chemo – unfortunately that turned into a three-hour delay. Then we had a delay on the saline drip for rehydration, which added another additional hour” (AC Cycle 4, August 19, 2014).

    As we became more familiar with processes, we became more efficient with our time, developing strategies to reduce the amount of time we spent waiting. When I became more confident in myself as a patient advocate, I learned to identify problems in the system and articulate them to management in hopes of resolving the issue. For example, in Learning to assert myself, (October 29, 2014), I write:

    Today, I asked for a supervisor.
    You see, I had an appointment. The online system showed my appointment as 9:15. I was told to arrive 30-minutes prior to my appointment (which is a bit excessive). I arrived 25-minute prior to my appointment (8:50). When I was still waiting at 9:30, I went to talk to the receptionist. Anytime I’m asked to wait more than 15-minutes, I want to know why I’m waiting (that is a lesson I have learned here – in Canada I would just wait in silence – it is interesting how asking goes against my ingrained behaviour). I found out that my actual appointment was at 9:45. The online system had already added 30-minutes, and the person who made the appointment for me added another 30-minutes. This is in part why patients spend excessive amounts of time waiting.

    Summary

    Nursing research shows that supporting breast cancer patients with navigating the healthcare system can improve many aspects of the care that patients receive (Robinson-White, Conroy, Slavish, & Rosenzweig, 2010). My analysis of the category Navigating the healthcare system shows that I had regular interactions with the healthcare system, and there were spikes in my interactions associated with receiving pathology results, starting chemotherapy, exploring surgery options, and surgery itself. Under the category Navigating the healthcare system, I constructed the following four themes: (1) learning processes, (2) taking control, (3) dealing with insurance, and (4) waiting. As I learned the processes associated with receiving cancer care, I wrote about them. When I was able to, I sought ways that I could take control over my interactions with the healthcare system. Unfortunately, there were two areas of challenge with my experience with the healthcare system, dealing with insurance and what felt like unnecessary waiting.

    Each person experiences breast cancer differently. This difference is in part related to the variable nature of the disease, but also the different healthcare systems where the patient is seeking treatment. The nursing profession has attempted to address this complexity with the creation of formal nurse navigators that help guide cancer patients through the healthcare system (Case, 2011). Unfortunately, not all healthcare systems have nurse navigators. In addition, the nurse navigators are often not fellow breast cancer survivors. This means that they cannot fully appreciate what it means to live with the illnesses associated with breast cancer and its treatments. The nurses are also insiders within the system, with knowledge and privileges that patients do not have. This can lead to a gap in what information the patient needs. Patients experiencing critical or chronic illness have a need to learn how to navigate the healthcare system from a patient perspective.
  • Learning about the disease

    Learning about the disease

    This post is a continuation on my discussion about Patient Health Literacy. The narrative that resulted from this study has been published on Amazon. See my Memoir page. The original source that I used for my study can be found at https://bcbecky.com.

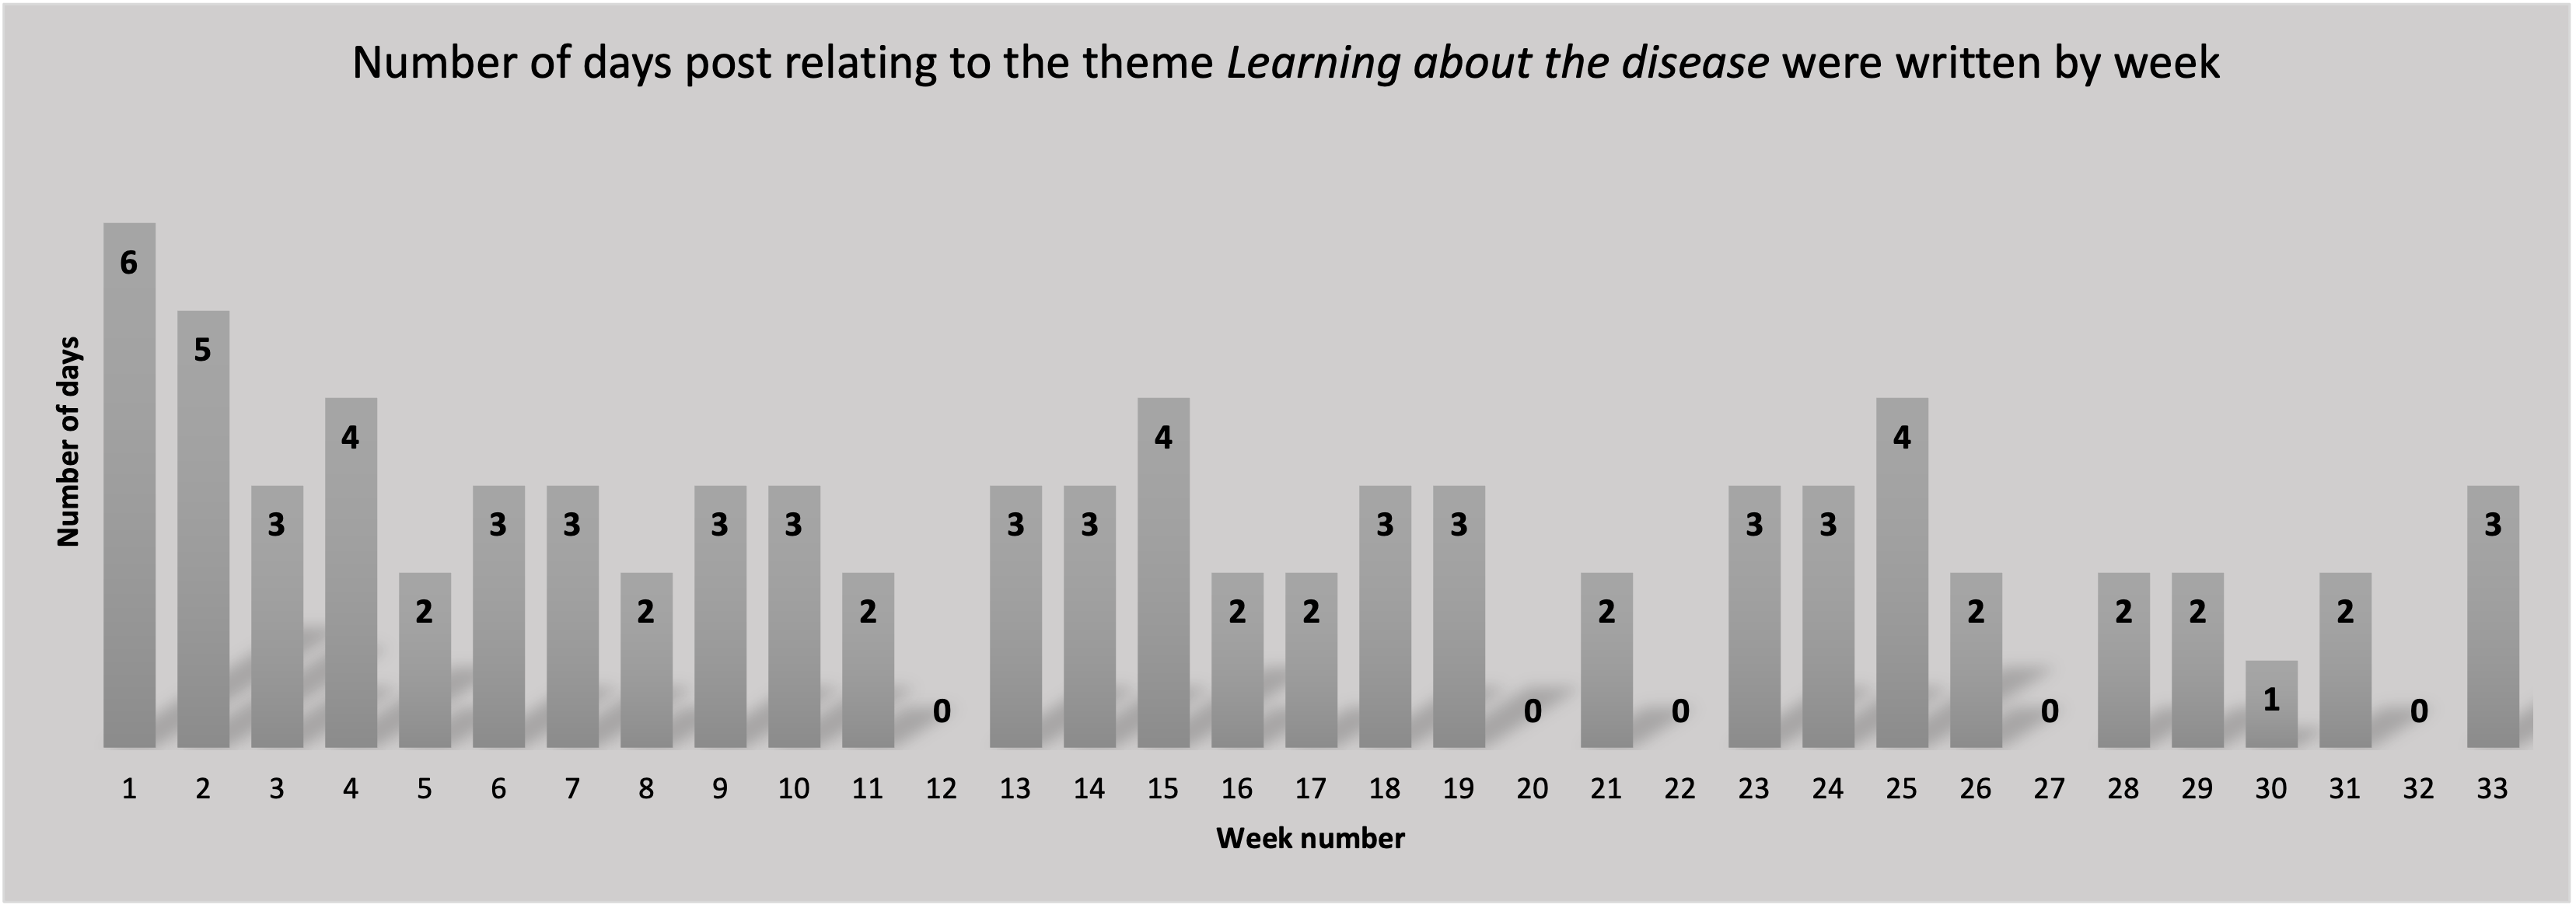
    From among the 237 blog posts, I coded 92/237 (38.8%) with the category, Learning about the disease. The distribution of number of days per week that I wrote one or more posts that were coded as Learning about the disease, Figure 4, shows interactions almost every week. This is particularly interesting because it shows that the learning did not just happen at diagnosis, rather I continued to learn and share my learnings throughout the study period.

    Number of days per week that a post was written that has been categorized as Learning about the disease.

    In reviewing the posts categorized as Learning about the disease, I constructed the following themes: (1) sourcing experts, (2) sourcing the Internet, (3) sourcing academic articles, and (4) sourcing peers. The theme sourcing experts applies to posts where I echo the information I receive from healthcare providers. The theme sourcing the Internet applies to posts where I include information from trusted Internet sources. The theme sourcing academic articles applies to posts where I include references to academic literature. The theme sourcing peers applies to posts where I describe information that I have gathered from peers such as through support group meetings. Peer sources includes blog posts of other cancer survivors. I discussion each of these themes in more detail in the in the following sections.

    Sourcing experts

    When I was initially diagnosed, I knew very little about breast cancer. In my early posts I would parrot back of the words I heard from my healthcare providers. For example, in It all started (June 14, 2014) I say, “I’ve been told that the majority of women who get breast cancer do not have relatives with cancer”. As I gather more specific information, I include my interpretation and feelings associated with the information I’m receiving. For example, in Double-Mastectomy and chemo (June 19, 2014), I write not just about the disease characteristics, but also what those characteristics mean and how that translates into a treatment plan. At this point, I am echoing the information the I received from an oncologist. I’m not referencing any other source. More importantly, in this post I’m not just talking about the data itself (that is the pathology), I’m also talking about what that data means and how that information affects the recommended treatment options.

    Sourcing the Internet

    Within support groups, I often heard the women say to someone who is newly diagnosed ‘do not look at the Internet’. And yet, it was the Internet that I went to when I needed to look up medical terminology. When interpreting my pathology report, I tell readers of my blog that if they want more information on how to understand pathology reports, to look at http://breastcander.org. I refer to this site several times within the blog, as it provided useful information regarding breast cancer and treatment options.

    When I wanted a description of medical terms, or when I wanted to validate something that I heard from either support groups or healthcare providers, I went to trusted sites on the Internet. In Significance of dates and getting ready for chemo (June 26, 2014), I write about my reflections on the chemotherapy preparation class that my husband and I attended. I share a couple of resources: a book that I found to be not very useful; and, a website, http://chemocare.com, that was very useful. I find it particularly interesting that advice is often given to ‘not look at the internet’, and yet the better and more current resources shared are those found on websites rather than books, which quickly become outdated.

    Sourcing academic articles

    Initially, I was unable to read academic sources, rather, I relied on my husband to do that research. However, when I had to make a decision regarding surgery, I reached into the academic literature to do an analysis on what the surgery and the expected results of neoadjuvant chemotherapy. For example, in Breast reconstruction – academic analysis (September 22, 2014), I write about the knowledge I gained through reading academic articles relating to the type of breast reconstruction surgery I was debating. In addition to sharing some of the key findings from the academic articles, I also shared terminology definitions such as “Autologous reconstruction is reconstruction that involves the patient’s own tissue (e.g. DIEP flap, TRAM flap).” In Pathological Complete Response (September 23, 2014), I write about the knowledge I gained, and my interpretation of academic articles associated with the expected outcomes of neo-adjuvant chemotherapy. I not only provide key findings, but I provide my commentary on the findings. I’m sharing both the findings from the articles and my interpretation of that information and how it applies to my situation.

    Sourcing peers

    In addition to healthcare providers, friends connected me to a fellow breast cancer survivor. I see echoes of conversations I had with here in my blog, for example when I say “choose who you want to trust, and then trust them” (A long day, June 19, 2014). By the time I was to start treatment, I was familiar with some of the expectations around treatment. For example, in This too shall pass (July 16, 2014), I say that “during support group last Saturday, one of the ladies explained what the Neulasta bone point felt like. I had been warned.”

    Perhaps the biggest benefit from support groups was the normalization of medical terminology and the generic breast cancer treatment process. Specifically, in A photo shoot and getting ready for surgery (November 18, 2014), I write about the process of the surgery. I specifically talk about the “injection of some nuclear isotope into each breast that helps to identify the sentinel node, and the insertion of wires to guide the surgeon to the exact location of each of the tumors”. By the time I wrote about the procedure, the concepts had been ‘normalized’ for me. I had heard about it so many times at support group that I came to think of the process as ‘normal’. It was just something that I needed to do. Further, in Breast reconstruction – Academic analysis (September 22, 2014), I point to another blogger’s post before I refer to the academic literature: “First off, I should start by pointing out an important blog post written by Nancy Stordahl on why breast reconstruction is not a boob job (2013). When looking at patient satisfaction, I focused on post-cancer reconstruction which is a lot more complex than cosmetic reconstruction.”

    I don’t share a lot of the medical information that I received in support group. In part because I often validated this information with my healthcare provider and then reported it in my blog as being from my healthcare provider. In Flyin’ (November 26, 2014), I write about information that I learned from various support groups pertaining to lymphedema, and then how I looked into the academic research about it, sharing some key points from the research. Here I am showing how the information I received through support group helps me know what to look up, but also how I do not directly trust the information in support group, rather I look to more trustworthy sources.

    Summary

    In order for patients to be partners with their healthcare team in making appropriate decisions, patients need disease-specific information (Wallberg et al., 2000). When I was diagnosed, I knew almost nothing about breast cancer. I needed to use multiple sources in order to learn about the disease. My analysis of the category Learning about the disease shows that I continued to learn about the disease throughout the treatment process. Under the category of Learning about the disease, I constructed the following four themes (1) sourcing experts, (2) sourcing the Internet, (3) sourcing academic articles, and (4) sourcing peers. Within these information sources, I did not only share the information directly, I also shared the way in which I was interpreting the information. In addition, as time progressed, I increased where I received my information, using multiple sources to validate what I was learning.

    I began my learning about breast cancer through information I received directly from expert sources, that is my healthcare providers. When I needed clarification on terminology or more detailed medical information, I sought out trusted Internet sources. When I was ready to read academic literature, I searched the literature for information that would help me make treatment decisions. The different information and advice sources sometimes overlapped, where at other times they didn’t. I had to learn how to discern not only where I could get information, but also what types of information I could get from where, and how reliable that information was. There were so many nuances to information that I didn’t always appreciate at the time, and some that I still don’t appreciate. Throughout the process I negotiated the information that I received from expert sources, Internet sources, and academic sources. Although I gathered information from peer sources, I did not directly trust that information, rather I used trusted sources to validate what I had learned through peer sources. Patients experiencing critical or chronic illness have a need to learn appropriate sources for different types of information to help them learn about the disease and what it means to live with the disease.

    Where do you find your health information? What sources do you find reliable? Where do you learn about how to live with the disease?

  • Developing Coping Mechanisms

    Developing Coping Mechanisms

    This post is a continuation on my discussion about Patient Health Literacy. The narrative that resulted from this study has been published on Amazon. See my Memoir page. The original source that I used for my study can be found at https://bcbecky.com.

    From among the 237 blog posts, I coded 163 (68.8%) with the category, Developing coping mechanisms. The distribution of the number of days per week that I wrote one or more posts that were coded as Developing coping mechanisms, Figure 2, shows that from the very beginning and throughout treatment I blogged about coping mechanisms. There are dips that align with the weeks where I wrote fewer posts overall and can be attributed to times where I was travelling or having surgery.

    Figure 2: Number of days per week that a post was written that has been categorized as Developing coping mechanisms.

    In reviewing the posts categorized as Developing coping mechanisms, I constructed the following themes: (1) blogging, (2) exercising, (3) social networking, and (4) seeking control. The theme blogging applies to posts where I write about or reflect upon the act of blogging. The theme exercising applies to posts where I write about exercising including hiking and being in nature. The theme social networking applies to posts where I write about connections with others that provide me support. The theme seeking control applies to posts where I am writing about ways that I try to find aspects of disease experience where I can create a sense of control. I discuss these themes in more details in the following sections.

    Blogging

    In the beginning, I highlight that I began blogging as a way to share my thoughts, as I was a blogger before diagnosis, I found myself wanting to write and share my experiences as a way to process what was happening to me, specifically I say “I shall look at this blog as a journal into lived experience, combining medical jargon with lived-experience of someone with breast cancer” (It all started …, June 14, 2014). A few days after diagnosis, I discovered another benefit to blogging, specifically that I didn’t have to keep telling people what was going on. I wrote “Mostly I’m pointing people to my blog, just so I don’t have to keep saying it. There is an emotional toll that occurs on both sides. Some people want to reach out and talk, but I’m not there yet. I cannot talk about it.” (A tough day, June 17, 2014). Later, I write about my intention to use my blog as a way to exercise my brain when I was worried about the effects of chemotherapy on my cognitive function. I wrote: “I shall keep up my ‘exercise’ and try to write regularly. I can only hope that my words continue to make sense and continue to demonstrate some level of cognitive competence” (Reflection on chemo brain, September 15, 2014).

    I talk explicitly about the blogging process at the beginning of the treatment process, but then stop writing about the blogging process as treatment progressed. This suggests that my reflections on blogging itself became normalized as treatment progressed, that is, that I no longer felt it necessary to reflect on how blogging was affecting me. 

    Exercising

    From the beginning, I recognized exercise as a priority, noting that I wanted to get as strong as possible before treatment began. Specifically, I say:

    My number one priority pre-surgery is biking. That is, back when I thought I might have cancer (after my family doc appointment) the one thing I decided was that I would train so that I was in the best physical shape possible before surgery/chemo. I want to make sure I’m going into this as strong as possible. For me this means allocating 2-3 hour a day (or more) for biking.
    (Priorities, June 18, 2014).
    Tweet

    As time progressed, I added hiking to my repertoire of exercise. I especially found exercising in nature as a way to feel both physically and mentally better. I highlight the effect of hiking in a grove of ancient redwood trees:

    I find peace in nature, so today we spent some time communing with nature. We went for a walk in the Redwoods up at Big Basin Redwoods State park. We walked for 9km, that’s a record for me. Big Basin Redwoods is perhaps one of my favourite places. The trees are literally 1000s of years old. There is a peace when you are walking and touching these ancient trees – some with battle scars from fires long past. They are survivors.
    (Why me? … it is what it is, June 23, 2014)
    Tweet

    Unfortunately, the side effects of chemotherapy caught up to me as I had mouth sores that made it impossible for me to effectively hydrate, which in turn curtailed my ability to exercise (Not talking = not blogging, August 30, 2014). After surgery, I returned to regular exercise as a way to recover:

    Recovery is still a long road. My hematocrit tanked again (lower than ever). I find myself easily out of breath while walking or climbing a single flight of stairs. My incisions are healing well. I still have a couple of drains which I’ll probably have until next Monday as they are still producing a fair amount of fluid. For the next week, we shall take one step at a time, trying to increase my walking distance and awaiting the day when I can get back on the bike.
    (The end of active treatment, December 29, 2014).
    Tweet

    Further, post-surgery I was thankful for all the time I spent exercising during chemotherapy, because “when I took my first steps, my legs were strong. It made a huge difference to how quickly I was able to move, and how quickly I’ve been able to walk.” (A small cup of coffee, January 2, 2014).

    Social Networking

    Initially, I was very hesitant about joining any breast cancer communities. It was my husband who pushed me to attend my first support group meeting, only a few days after my diagnosis. In Support group (June 22, 2014), I express how attending the support group helped me learn to talk about my cancer. I had to say it out loud. It also gave me a space to talk about breast cancer with others who understood what I was going through.

    Further, in Joining the cancer blogsphere (July 6, 2014), I expressed my hesitation in joining the breast cancer blogosphere:

    I have strong online relationships. I am part of several online communities where I find strength and much needed support. But, to join a cancer community means to admit that I have cancer – but there is more to it than that – it is the fear of joining a community and then losing people in that community. I’m OK with admitting I have cancer, but I’m not OK with admitting that it is something that might one day kill me. I’m afraid that if I develop solid friendships with others who have cancer, that I’ll lose them. I don’t want to have to deal with the death of a good friend – and so, I hesitate. I hesitate to reach out too much to others who are also going through this experience – not because I don’t want to meet these people or get to know them – just that I don’t want to get to know them and then lose them.
    (Joining the cancer blogsphere, July 6, 2014)
    Tweet

    Despite my hesitance to reach out to new support communities, my posts show that I did reach out to my pre-existing social networks for support. For example, when I found that I needed support to overcome inertia and side effects in order to exercise, I called on friends to help keep me accountable and help me get off the couch using a personal Facebook exercise support group (Significance of dates and getting ready for chemo, June 26, 2014).

    Further, the importance of social networking as a coping mechanism was suggested when I blogged about the role of social media in my process of gathering information about breast cancer and treatment options. In Social media and patient engagement (October 29, 2014), I outline what type of information I gathered from social media:

    I have been reflecting on social media and the type of information I get from social media. I use social media to get a sense of the ‘lived experience’ of a given treatment. When I reach out and ask, I receive experiences from others as well as a boat load of advice. This information is often very useful in helping me better gauge what to expect, but also in helping me ask questions of my healthcare team.
    (Social media and patient engagement, October 29, 2014)
    Tweet

    In addition to using my social network for outside support, my blog also highlighted the importance of having a caregiver to provide support when I was not able to make decisions for myself. The impacts of cancer and chemotherapy on my mental capacity meant that I could no longer troubleshoot when unexpected events occurred. My husband, Scott, was my rock and was there to ensure continuity of care. After my first surgery, where he could stay the night in my hospital room which “turned out to be very useful, as several times I benefitted from having a patient advocate (things like helping when I needed to use the toilet). It also meant that he was here for most of the doctor and nurse visits.” (An update from the hospital, November 20, 2014). Further, caregiver support was highlighted when I blogged about the challenges of returning home after my second surgery:

    When we got home one of the biggest challenges was figuring out all the medications and a schedule that allows us to create an efficient process. I can now better appreciate why it felt like the nurses were giving me various pills on an almost hourly basis. Someone asked how many? I’m at 17 different meds, with 11 different dose times. The goal in setting up a schedule was to optimize pain medications and reduce the number of times in the day I’m taking drugs, while still respecting various drug interactions. This isn’t something that is easily done by the pharmacy, as the pharmacy doesn’t deal with all the over-the-counter meds that are also prescribed (e.g. I’m prescribed certain vitamins which aren’t provided by the pharmacy).
    (Getting organized at home, December 23, 2014)
    Tweet

    Seeking Control

    Initially one of the ways I exhibited the theme seeking control was through intentionally finding ways to have fun. This became an explicit activity. I knew that if I didn’t find ways to have fun then treatment would be very difficult: “One of the things that causes that natural high for me is sailing. So, we are looking for ways to go sailing regularly. However, sailing can be very physically demanding, which will likely be a challenge. This Saturday, we are headed up to the city to go sailing on a 2003 America’s Cup boat.” (Priorities, June 18, 2014).

    In addition to intentional fun, I also had to explicitly give myself permission to do things. Initially, it was giving myself permission to nap (I had to give myself permission to nap, July 9, 2014). As the idea of surgery approached “I have given myself permission to go into surgery kicking and screaming. I’m OK with not being calm and collected when I get rolled into surgery. It is natural to not want to deal with it.” (I’m scared, September 17, 2014).

    After I began chemotherapy treatment, one of the ways I attempted to regain a sense of control was to shave my head prior to losing all my hair. I explain this decision:

    If you haven’t done a chemo that causes hair loss you may not understand this idea of proactively shaving your head. There are a couple of reasons for it. The practical reason is that hair falling out in clumps is a pain. The second, more important one, is an exercise in control. If I’m going to lose my hair, then I am going to control when it happens. Control is a huge issue with cancer, as it is one of the things you lose. You lose a lot of control over how your body is growing, how it reacts, and the various schedules of appointments. When you have an opportunity to take control and do something on your own terms, it can be important for some people to take control.
    (In for an emotional day, July 17, 2014)
    Tweet

    Further, to help plan for chemotherapy side effects, I created a chart of my symptoms, see Image 1, which I used to help predict when I was going to experience the different side effects in future chemotherapy cycles. I also used the chart to determine which steps I should take to proactively reduce the impact of the side effects (Mouth sores & first cycle symptoms, July 20, 2014).

    Image 1: Chart indicating the timeline of anticipated chemotherapy side effects.

    Perhaps one of the more pragmatic attempts at seeking control was through planning. Unfortunately, the unpredictable nature of chemotherapy treatment meant that some of the plans I had originally made, specifically my original plans for a trip to Hawaii, would no longer work. Additional planning was required regarding the new treatment schedule:

    I’m actually of quite mixed emotions. This plan works for me – it lets me still get in a trip to Hawaii before the first surgery, and a trip to visit my parents before the second surgery. We ran through the schedules last night, and it even looks like my friends from Nova Scotia can still join us in Hawaii (yay). The extra chemo gets me that much closer to finishing the protocol (which calls for 12 sessions of Taxol – in the end I’ll have 9 sessions). Part of me doesn’t want the extra two chemo sessions – I’d just like to stop chemo and go on with the surgery, but another part says – what if those extra two are the difference between beating this thing and not? Will those two extra sessions be extra insurance against recurrence? Metastasis? Of course, we don’t know. We have no way of knowing whether or not a couple more sessions of chemo will make any difference what so ever. But to align with the surgery schedules, it is best that I am in chemo right up until three weeks before surgery. And then I get four weeks between the first surgery and the second surgery. I’m happy for a little extra time to ensure that I’ve healed.”
    (Temper tantrums, October 15, 2014)
    Tweet

    Finally, the post-surgery posts in seeking control relate to advocating for myself during interactions with the healthcare system. Specifically, I wrote about negotiating with a resident regarding a surgical side effect, and my unwillingness (non-compliance) to take her recommendation:

    Sensing my non-compliance, she asked if I was okay with the plan. I said “no, how about we watch and wait? — because I am passing some urine, I’m not completely blocked — it is just taking time and not flowing properly”. I don’t completely trust the resident’s opinion. I want to hear it from someone with more experience.  
    (Ya no!, November 23, 2014)
    Tweet

    Summary

    One of the important aspects of health-related self-efficacy around cancer care is the need for the patient to develop coping mechanism (Papadakos, 2017). In my theme analysis of the category Developing coping mechanisms, I show that I continually developed coping mechanisms throughout treatment. Under the category of Developing coping mechanisms, I constructed four themes (1) blogging, (2) exercise, (3) social networking, and (4) seeking control. Blogging was initially a way in which to help me process and share my treatment decisions. Later, blogging became a way of exercising my mind, where physical exercise provided a way for me to feel physically and mentally better. Throughout the study period, I found support in both face-to-face and online social networks. The theme social networks also included support that I received from my husband and primary caregiver. Finally, I blogged about the ways in which I sought control, including intentionally planning fun activities and travel. Control seeking was also expressed through self-advocacy.

    My analysis of the category Developing coping mechanisms showed that I continually developed coping mechanisms throughout treatments. Although each individual chooses to cope in different ways (Al-Azri, Al-Awisi, & Al-Moundhri, 2009), blogs such as mine provide a great resource for discovering what coping mechanisms might be useful. A practice that I developed through my experience was to develop coping mechanisms such as blogging, social networking, exercising, and seeking control. Patients experiencing critical or chronic illness have a need to develop coping mechanisms in order to learn how to live with illness.

    References

    Al‐Azri, M., Al‐Awisi, H., & Al‐Moundhri, M. (2009). Coping with a diagnosis of breast cancer‐literature review and implications for developing countries. The breast journal15(6), 615-622.

    Papadakos, J. K. (2017). The Association of Health Literacy and Self-Efficacy to Cancer Chemotherapy Self-Management Behaviours and Health Service Utilization. Doctor of Philosophy.

    Are you a patient? Do these coping mechanisms align with your experience? What other types of coping mechanisms did you develop?

  • Never knew I wanted to be a breast cancer survivor

    Never knew I wanted to be a breast cancer survivor

    I have finally taken the leap and published my breast cancer memoir: Never knew I wanted to be a breast cancer survivor.

    This memoir began as a Autoethnographic PhD study. I analyzed the first year of blog posts written on BC Becky, my breast cancer blog. My analysis involved constructing themes. The themes helped me choose which of the blog posts made their way into the book. Over the next several blog posts, I’m going to share the results of my analysis. For starters, the themes I identified are:

    • Developing coping mechanisms
    • Navigating the healthcare system
    • Learning about the disease
    • Understanding side effects
    • Advocating
    • Exploring body image
    • Making decisions
    • Negotiating identity

    I came to the conclusion that these themes aligned with patient health literacies that I developed throughout my treatment experience.

    Patient Health Literacies – (c) 2020 Rebecca J. Hogue

    If you are reading the book, can you see these themes? Do you see any other themes in the book?

  • How do you describe something you chose not to finish?

    How do you describe something you chose not to finish?

    I spend the better part of the last 9 years working on a PhD. A lot happened in that window. A lot of life changing transitions. I was diagnosed with breast cancer, I lost my father, and then a year and a half later I lost my mother. These each had a profound impact on who I was.

    When I started the program my goals in life were very different than they are now. I had planned on spending only 5 years working on a PhD – but cancer had a different idea. Then I had to start over. Through that process I have learned a lot. I have grown as a person. I have grown as an academic.

    Just before the covid lockdowns started, I decided that I was done working on the PhD. I was looking at another year of writing and revising and giving up my free time working to jump through academic hoops that I didn’t see as helping me move forward in life.

    At the end of April I official withdrew from the PhD program. I am no longer a PhD student. That feels weird to say because it was such a large part of my identify for a very long time.

    Unfortunately, we don’t have a way to celebrate that accomplishment and we don’t have a way to talk about it. In academic settings, I might use the PhD (ABD) term, only to help people understand that my education is beyond that of a masters.

    I updated my linked in to show that I had finished my time at uOttawa. I did not add a degree. However, this caused LinkedIn to tell all my friends that I had “finished at uOttawa”. I got several congratulations type messages – at first thinking I had to write back and explain that I didn’t get my doctorate. I just stopped being a student. It felt awkward.

    And now, with the next semester about to start I’m in the situation of having to describe myself to my students. I am at a loss for what to say, as I am no longer persuing a PhD in Education, nor have a completed a PhD in Education – but the work I have done over the last 9 years wasn’t nothing. I learned a lot, and I have a much deeper understanding of a lot of concepts as a result of my time studying. But I don’t have a way to “label” the work that I have done.

    I find myself wanting to just leave off references to the PhD, almost like I am trying to erase the work that I have done over the last 9 years. I am afraid that by walking away, it is seen as a failure – that I failed my PhD – which is not what happened. I chose to walk away from it. I chose to do other things with my time. I did not fail it.

    But I am not being fair to myself when I ignore the last 9 years. The work that I have done over the last 9 years counts for something. It has shaped who I am as a Lecturer and who I am as a person. It isn’t part of me that needs to be erased. So I do I honor that time?

    After walking away from PhD studies, how to you describe what you have done?

    Feature image by Evgeni Tcherkasski on Unsplash

  • A different lens #patientnarratives

    A different lens #patientnarratives

    An article in the BMJ blog about The transformative power of patient narratives in healthcare education crossed my stream today. This timing could not be more appropriate as I am working on the discussion for my dissertation and working through the concept of health literacy.

    From the article, Baines, Denniston, and Munro (2018, July 8), highlight three ways that patient narratives have value in healthcare education:

    1. we should not deny the subjective nature of patient narratives; it is not a weakness, but a strength
    2. we should strive to improve the opportunity and accessibility of narrative provision and receipt for both patients and educators
    3. we should seek to develop a culture of value, acceptance and transparency

    The issue of value is the one that I have struggled with. I look at my illness blog and know that it has value. It has been valuable for me as a patient, but also valuable to many other patients. The illness blog genre helps patients better understand what it means to live with illness and how to cope with the various side effects of illness and treatment. One might argue that there is valuable medical knowledge within the blogosphere.

    That being said, I am also taking a totally different lens when I look at the value in patient narrative. I am not looking at it from the perspective of the healthcare system or medical education. I am not arguing for the value in that context. I leave that to others. I am arguing that the patient narrative has value to other patients (and caregivers, family, and friends). The patient narrative focuses on the illness experience, not the disease. Medical education and the healthcare system is focused on the disease. In many ways, the illness experience is beyond their scope.

    I agree that there is value in patient narrative for medical education – but the value is different. It is looking at the illness experience through the lens of treating the disease. Where patient narrative and peer-to-peer sharing of experience can help patients better live with illness. It can help patients understand what it means to live with illness. If you haven’t experienced it, then you don’t understand it in the same visceral way that someone who has gone through it does.

    For a lot of my early stages of research, I was frustrated with needing to make the argument that patient narrative is valuable. I struggled with the frustration of the ideas of “evidence based” and “gold standard”, which all equate to quantitative (measurable), as being the only form of value in medicine and medical practice. I wanted to scream to say that illness experience matters too. My experience could help you be a better doctor. But now, I realize that I am making the wrong argument. I do not need to participate in that particular struggle. To me, the greater value in patient narrative is in the value it provides to other patients who are struggling to learn how to live with illness.

    Feature image by Valentin Salja on Unsplash.

  • The relationship between oppression and empowerment?

    The relationship between oppression and empowerment?

    Is there a relationship between oppression and empowerment?

    I am noticing that as I code my research narrative that often even within the same post, I write about an oppression but then I write about what I am doing to empower myself as a result of the oppression.

    Take for example my blog post entitled How do I be an ‘engaged patient’ in a hospital gown? (September 27, 2014). In the post I describe the challenge as a patient when wearing a hospital gown. I explain how the declothing and gowning is an oppression, especially when the patient is left in the gown unnecessarily – throughout the entire consultation.

    Within the same post I also describe my solution to the problem. I describe how I bring a hoodie and wear that over the gown. I have a zipper, so that it can be easily removed when it needs to be, but also can be easily put back on, so that I’m dressed throughout the interaction. I create a way to empower myself as a reaction to the oppression. 

    Is empowerment needed if there is no oppression? Can there be empowerment without oppression?

  • Oppression of the disease and its treatment

    Oppression of the disease and its treatment

    In looking at health literacy from a socio-cultural and critical perspective, one of the themes I’m looking at is oppression. I had originally thought that I’d be looking at my experience and how the healthcare system (e.g. providers, insurance companies) was oppressing me – although I questioned the term oppression in part because the healthcare system was also providing me with care. There were some aspects of the system that were setup to privilege the providers at the cost of oppressing the patients (e.g. the excessive amount of time patients spend in waiting rooms). This is where I thought I would be going with the theme of oppression.

    My work doing actor-network theory research has shown me how non-human actors (in some cases objects or software) can have influence. As I re-read through my research narrative, it occurs to me that in the same way as software can influence behaviour, the disease itself can be a non-human source of oppression, as can the treatment for the disease. Yes, these things are created by humans (but then so is software), but the actor (or influencer) of the phenomena under study could be a non-human actor.

    “It started at about 5pm last night, I felt these pulsing pains up my spine. By 8pm last night, they were excruciating whenever I was in the seated position.” 

    (This too shall pass, July 16, 2014). 

    Now, as I re-read through my research narrative, more so than the healthcare system, I see additional causes of oppression – the disease itself and the treatments for the disease. Initially, I had only been considering the actors as those that were people or corporations. I had not considered that in a healthcare sense, that there were non-human actors — diseases and treatments.

    When I look at the disease and treatment, I can see clearly the oppression that they exerted – and even four years later they continue to exert. I no longer have a question about whether or not the word oppression is an appropriate one. With breast cancer, both the disease itself and the treatments for the disease are sources of oppression.

    Feature image CC0 via Pixabay.

  • My experience of health literacy

    My experience of health literacy

    I had a realization the other day that will help with the final sections of my dissertation.

    The current, most often cited, definition of health literacy is defined by The National Academies of Sciences, Engineering, and Medicine (2004) as:

    “the degree to which individuals have the capacity to obtain, process and understand basic health information and services needed to make appropriate health decisions” (p.16). 

    Further, Digital Health Literacy, is defined at:

    “the ability to seek, find, understand, and appraise health information from electronic sources and apply the knowledge gained to addressing or solving a health problem” (Norman & Skinner, 2008, para. 6).

    I had thought that in my dissertation I was looking to redefine health literacy from a patient perspective. I had thought that what I was trying to create was something that might be adopted by others. However, I now realize that I’m not looking at a general definition. I’m looking to figure out what my definition is.

    I know that the research I’m doing is interpretive, and in no way am I trying to make generalizations, and yet, I had not internalized that when it came to this definition. I had thought that when I get to writing my discussion chapter that it would all just come together and I’d have this magic definition that would be adopted or something. But that doesn’t make sense. What I will have is my story and my experience of health literacy. It won’t even be a definition – rather it will be an articulation of experience that I somehow abstract into a conceptual framework or something like that.

    I’m looking forward to getting to that chapter. I’m currently working on a chapter that looks at my experience of health literacy through the lenses of critical literacy and socio-cultural literacy. Once I’ve done that, I will take everything that I’ve written and analyzed, and somehow bring it all together. That is the part I’m looking forward to – that building of some conceptualization based upon my themes and the different lenses of the story. It is nice to be excited about my dissertation again 🙂

  • And alternative CV #unboundeq #altcv

    I have been reflecting on the alternative CV activity in the Equity Unbound course for over a week now.

    I tried to do something visual, but that just wasn’t working for me.

    I found myself asking, what are my values? Or, what am I most proud of? Right now that answer is that I was seen as a good caregiver and a good friend. Those mean the world to me. So much more than any academic credential.

    I’m trying to figure out how to look forward, and figure out what I want my new CV to look like. I’m still working on self-care, after a traumatic 5-months of caregiving.

    Another blog that I follow, asked the question What is your greatest strength? I too have been thinking of this. What comes to my mind immediately is cooking. Again a form of hospitality, a form of caregiving.

    Now, for the alternative CV, I want to link those values to what I do – which is teach. I see now that is an important part of my teaching practice is hospitality. It is making students who are nervous or uncertain feel comfortable, and then building up their self-confidence. When they leave my class, I feel like I have succeeded if they leave with a sense of pride and amazement of what they achieved. It is they that did it, not me. I simply gave them the opportunity to demonstrate their potential. I love that.

    I’m still figuring out what I’m going to do with my life now, but I’m moving forward. I’m working on some self-care. I’m teaching again and loving it. It still feels like every day I’m lifting sandbags, but with each day the bags are getting lighter, and I’m moving just a little bit faster.

    Perhaps, that is my greatest strength – tenacity. Sometimes progress is slow and frustrating, but I keep going – and with that, I’m headed out for a hike 🙂

  • Greater themes

    In reading today’s post by Carolyn Thomas at Heart Sisters, she talks about a show on CBC Radio (Michael Enright’s Sunday Edition), and how the interviewer highlighted that illness narratives were not just about the facts of the illness, but also addressed bigger life questions.

    That got me thinking about what my illness narrative is about, and what might make it interesting not just to those who have breast cancer, but also to a more general audience. Dealing with a critical incident, that has you contemplating your own mortality certainly brings in themes of larger life questions.

    One of the themes that I have in life is the tension between “living for the moment” and “saving for the future”. This is a constant theme in my life – but I’m not sure that comes out in my dissertation draft of my illness narrative. That narrative is too focused on the acute time in treatment when there is no plan for the future, as there is no ability to think beyond a 2-3 month horizon. I recall after active treatment struggling with how to think and plan for events beyond three months.

    One of the big life themes that I do address is that of exploring and expressing my values and how my values directly affect my treatment decisions. This really shows in my struggle to decide on breast reconstruction. I struggled with the role my vanity was playing in the decision. I recall the anger and arguments I was making, and realize that I was working really hard to convince myself of the decision, but the decision didn’t feel right inside. In the end, with the help of my surgeon, I changed my mind. I am thankful for that help. I can think of how others might interpret her behaviour as pushy, but for me it was the push I needed to really test my conviction in the decision I had made. I’m glad that I changed my mind.

    That brings me back to themes. I need to do some more thinking on the greater themes. My dissertation really focuses on the “knowledge” related themes, looking at what knowledges I was imparting on my blog. It doesn’t delve deeper to look at the larger life themes that I’m addressing. I am not wondering if that is part of the discussion that needs to happen in my discussion chapter (the one big chapter I have left to write). The change in focus that highlights that the story isn’t just about the knowledge that is being imparted, but that the illness story is also about larger life questions.

  • An update, a bit about project LEAD, and request for ed tech resources

    It has been a long time since I’ve posted to this blog. In April or May, we put my PhD on hold for 8 months so that I can care for my mother, who at the time was diagnosed with stage 4 kidney cancer. I lived with her most of the time, with a couple of short trips back to California to deal with my health issues, until she passed away on July 1st. Then we spend a couple of weeks trying to get her house and affairs in order. Since my dad passed almost 2 years ago, we are now in need of dealing with the estate. In many ways it isn’t that complicated, but still it is time consuming.

    I did do some academic professional development last week. I attended the week long Project LEAD Institute sponsored by the National Breast Cancer Coalition (NBCC). I learned a lot about the science around breast cancer as well as how different types of research are done. I’m particularly fascinated with epidemiology – it is a field that is exploding with access to new electronic data sources.

    This fall I’ll be teaching two classes at uMass-Boston: (1) Foundations in instructional design and learning technology, and (2) The design and instruction of online courses. It will be great to set students up for success in the program in the first course, and then see them again towards the end of their degree in the second course. I’m also looking forward to wrapping my brain around the latest trends in instructional design and online learning. Right now I’m feel a little out of touch – but I suspect that will change pretty quickly once I get back to some semblance of normalcy.

    If you have any suggestions for the latest trends in learning technology – what the hot tools of today – I’d be happy to hear your suggestions. What tools to you use in your teaching?

  • Relational and activity based identities

    I’m currently reading Teaching, Learning, Literacy in Our High-Risk High-Tech World: A Framework for Becoming Human by James Paul Gee (2017). In it, he talks about two types of identity (at least to the point that I’ve read so far).

    First is activity-based identity. These are the identities we have based about activities that we choose. For example, I’m a blogger. I identify as a blogger. This is an activity-based identity. It is based upon something that I do, and more so, something that I choose to do.

    Second is relational identities. These are based on categories that are attributed to us. For example, I am Canadian. That is a relational identity. I was born in Canada, and am a citizen of that country.

    In the world that I was thrust, I am also a cancer survivor. That is a relational identity. I did not choose to be a cancer survivor, rather, by nature of a diagnosis of cancer I became a cancer survivor.

    I chose to use that new identity as cancer survivor to become an ePatient (a patient who is equipped, enabled, empowered, and engaged in healthcare). Being an ePatient is an activity-based identity. I’m not an expert ePatient – not yet anyways, but I am an ePatient. It represents a group of people and culture in which I have chosen to be a part of.

    Now, Gee also talks about how sometimes we choose to reclaim relational identities to make them our own. I see this with cancer survivors all the time, trying to figure out what this new identity means, but also finding meaning in it. I chose to use the term cancer survivor, largely because it is something people understand. It isn’t a label that I would have chosen myself, but it does effectively tell people that I am part of the group of people who have experienced cancer as a patient.

    On a side note, at one point Gee mentions “Saint Simeon Stylites (A.D. 390–459) was an ascetic who lived for 37 years on a small platform atop a pillar near Aleppo in Syria. He inspired a 6-century-long succession of stylitoe, or pillar hermits (Lent, 2008).” (p.97). I thought I’d share a feature image of what was left of the pillar that Saint Simeon Stylites stood upon. We visited it in December 2008 when we were in Aleppo Syria.

    I’m not sure what all this means yet – just that I needed to write about it. I needed to blog about it – because I am a blogger and that is what I do.

  • Privilege and equity in health care

    I shared the other day the idea the for the privileged equity feels like oppression.

    It occurred to me that this is in part why I am scared at the idea of moving back to Canada and relying on the Canadian healthcare system. The Canadian system is a good one. It is mostly equitable. It suffers from the same issues as most, in that people in rural areas don’t get as good care as those who live closer to major medical centres. That issue exists in the US too.

    But, at the moment, I’m extremely privileged when it comes to healthcare. I have good insurance. For the most part, I have access to excellent doctors, and I can afford my medicines. I have learned to use my privilege to get good healthcare.

    Going back to a more equitable system means I will lose my privilege. I will need to learn to navigate a different system. I will still have some privilege because of my education, but it will be much less than I have at the moment, in the vary inequitable American system.


  • Precision social media support – an #epatient example

    In early January, I joined Christopher at Just Talking for a podcast. One of the topics that came up during the podcast was the role of social media (and in my case Facebook groups) as patient support when going through illness.

    I spoke of my experience with Facebook groups relating to my choices are breast cancer surgery. Early in my treatment I was certain that I was not going to opt for reconstruction. I joined this awesome Facebook group called Flat and Fabulous. The women in it were a constant source of support, not just around the decision to go without reconstruction, but also on other aspects of learning to live with breast cancer and managing side effects of chemotherapy. I know that at any time of day I could post a message and I’d receive encouraging and informative responses.

    When I decided that I would opt for reconstruction after all, I had to leave the flat and fabulous group. Their guidelines were clear – they were there to support those who chose not to reconstruct. They were not making any judgement or value statements, just that they have a clear niche and want to keep it that way. And so, I left the group, and found another group – this time, the group I sought out was one that supported the specific type of reconstruction surgery I was having. This too proved to be very valuable to me, as I had 24/7 access to women who knew what I was going through. When I had a weird symptom I could ask, is this normal? Is this something I should call my doctor about immediately? or is it something that can wait until the next appointment? The group helped me prepare for my surgery and helped me be better prepared for what I would be experiencing in the aftermath of the surgery – all the little (and not so little) things the doctors forget to tell you.

    What is interesting about this is that I was about to find Facebook groups that aligned with where I was in treatment, and that as my treatment changed, I was able to find groups that aligned with those changes.

    In the pod cast, Christopher mentioned a connection to the concept behind precision medicine. The idea being that rather than giving one treatment for everyone, that we use some characteristic (in the case of precision medicine it is molecular makeup of tumors) to determine treatment. So, it is isn’t a one-size-fits-all, but rather a more personalized approach. In some ways, social media can provide this. In my case, it was with Facebook groups – there are so many different Facebook groups around the different areas and treatments for breast cancer that I was able to move from one group to the next when I needed to. I could find one or more groups that supported me in the stage / phase that I was in. When the group no longer aligned with my needs (or treatment choices), I was able to find another group that worked better for me.

    It makes me wonder if others who use social media for health support, if they do the same thing? Is the movement from one group to the next common?

  • Health Literacy repositioned

    I recently read an article on health literacy by Uta Papen: Papen, U. (2009). Literacy, Learning and Health–A social practices view of health literacy. Literacy and Numeracy Studies: An international journal in the education and training of adults, 16(2-1), 19-34. Retrieved from https://epress.lib.uts.edu.au/journals/index.php/lnj/article/download/1275/1326.

    The dominant view is that health literacy is an ability possessed by individuals (Weiss et al 1995, Baker et al 1999, Nielsen-Bohlman, Panzer and Kindig 2004, Lurie and Parker 2007). It consists of a set of competencies transferable to different contexts. Because health literacy is treated as being context-independent, it is assumed to be measurable through abstract tests. Accordingly, there is much research into patients’ levels of health literacy, this being seen as a prerequisite for developing new tools to teach health literacy. ~(Papen, 2009, p.20).

    The measurable idea is an interesting one. There are a lot of research articles that ‘measure’ health literacy. One focus of health literacy research and practice is to look at how medical terms are labeled / described and to make the language used more patient friendly. I think this is a good thing, but it is also a vary narrow aspect of what health literacy is. It only focuses on the basic reading / comprehension aspect of health literacy but does not look at health literacy from the lens of self-advocacy / self-efficacy.

    Rather than the dominant (very post-positivist, anything can be measured) view, Papen takes a position on health literacy that approaches health literacy as a practice – and more specifically, a social practice.

    The study was grounded in a view of health literacy as social practice. Accordingly, we talked about health literacy ‘practices’ rather than health literacy ‘skills’. Setting aside the notion of skills, we were able to explore what people do with reading and writing rather than to ‘assess’ how good (or bad) they are are what they are doing. This is not to say, however, that we are not interested in people’s abilities. But we did not define these as narrow skills. Rather we conceptualized them as context-bound and changing competencies, some of which, as I will show below, were not located in individuals but in groups and social networks. ~(Papen, 2009, p.21-22).

    She takes this one step further, and looks at how health literacy can exist in networks – so not just in the individual. The idea is that when you have a health problem, you don’t just look to yourself for knowledge, sometimes the knowledge you need exists and is shared within your network. Your network is what contains the knowledge you need to make your ‘informed’ decision.

    …health literacy is often ‘distributed’. By this I mean that it is not simply a property or an attribute of an individual, but that it is shared knowledge and expertise. It resides in the patient’s social network. An individual’s health literacy could thus be seen as the sum of what she knows and is able to do herself and what she is able to achieve with the support from friends, family and other significant people in her environment. ~(Papen, 2009, p.27)

    Reading this brought me back to the connectivist learning theory, and the idea that knowledge can reside within networks, not just within people. One of the principles of connectivist learning learning is that ‘knowledge rests in networks’ – and this distributed definition of health literacy is an example of how knowledge exists within the network.

    Prior to reading this example, I didn’t really ‘get’ the connectivist idea of knowledge resting in networks. But now I do. I know first hand how my social networks helped to ‘inform’ my health decisions. I cannot say that one person or even a group of people help to inform the decision – rather it was the network as a whole, together. This too links to concepts of complexity, where the network together is more than just the sum of the parts – it is a thing into and of itself.


  • Experience, expression, and meaning making

    I’m finding myself in a bit of a challenging position right now. I don’t know if it is a funk – or just kind of stuck. Typically, when this happens I go for a nice long hike and sort it out while I walk and commune with nature. However, after recent toe surgery (which is healing nicely), I cannot yet walk – and so, I’m going to try to express some of my thoughts in writing.

    One of my research questions is “What was my lived experience as a breast cancer blogger?” I realize that even with my narrative chapter – written in the form of blog posts from my time in treatment for breast cancer, I’m not really answering the question. In part, I don’t talk to the blogging aspect of the question at all, but also, how can one express lived experience? I think I have asked an unanswerable question – which is written a little in academic-ese – as the term “lived experience” is something meaningful to academics and signifies that what I’m answering is an ethnography.

    In the book Networked Cancer: Affect, Narrative, and Measurement (Stage, 2017), the author asks “Should [illness] narratives be understood as expressing life with an illness”? The question here is that of expression rather than experience. Narratives are necessarily only part of the story. Some narrative embellish, while others gloss over. There is always a reason or purpose behind the narrative. The narrative can never be the experience. In that way, I’m not asked “What was my lived experience”, so much is “how might my breast cancer treatment experience be expressed as a blog-formatted narrative?” That, indeed, is the question that chapter 4 of my dissertation answers. Maybe, part of my challenge is that I’m struggling with a nebulous question, which then makes it more difficult to defend the answer.

    The next part of my dissertation looks at what knowledges I shared on my blog, looking at the question “What knowledges did I share through blogging about my breast cancer experience?” My blog itself (http://bcbecky.com) is the data source (not to be confused with the blog-formatted narrative). More specifically, I’m using the blog posts from June 14, 2014 through February 3, 2015 – all 237 of them! as data. I’m looking at what types of things I shared on the blog – what things that could be considered forms of knowledge. Now, one could devolve very quickly into a philosophical question of – what is knowledge – which frankly, would cause me to have my eyes gloss over and make me question why I’m doing this whole PhD thing anyways – but to get it back on track, I asked myself the question – “what types of things did I share on my blog?”, leaving the definition of “thing” rather loose – looking more for patterns than anything else.

    This is how I came to the major categories in my theme research – which I then looked at each theme in more depth and drilled down again – looking at subthemes.

    The problem I’m challenged with now, is looking at the data and analyzing it as if I were not the person who lived the expressed experience in the first place. I listen to other’s comments on some of my posts and am fascinated by how much they see in my posts – but then I realize what they are seeing is not what I was expressing – nor does it have any meaning for me. It is an attempt at making meaning from the text that is written, when what I’m trying to do is make meaning out of the experience I lived – and I’m not sure those two things align – maybe they do – maybe, I’ll think though it and push through the resistance I’m feeling, and it will all click together – it has happened before!

    The sentence that really sticks out is this “it is an attempt at making meaning from the text, rather than making meaning from the experience“. Perhaps, I’m coming back to an impossible question – just like it is impossible to answer “what is my lived-experience”, it may also be impossible for me to make meaning from the text – frankly, I always hated that part of English class, where we attempted to analyze novels and such – attempting to derive some deep meaning from a written text, when each person interprets the text differently (and I didn’t ever really clue in that the goal in school was to figure out what the teacher interpreted from the text, because it was never really my interpretation that was being solicited – but that is an aside).

    The question I have now to answer is, where it is that I’m trying to find meaning in this process? My supervisors tell me that I have to not just present the data/results, I also need to explain what those results mean to me – I need to describe the meaning. It is OK for others to see meaning in my text that is different than the meaning I see. When I doubt myself, it is often because I am doubting that I can ever see the same meaning as someone else is seeing – but I am realizing as I type, that I do not need to see the same meaning. That doubt (and impostor syndrome) comes from misunderstanding – it comes from a voice in the back of my head that is telling me that I’m missing the meaning that others see, and that somehow, the meaning that I see is less worthy / less valuable than the meaning that others see – when really, the goal is not to find “the meaning the teacher wants me to find” like back in high school, but rather to find my own meaning in the data. I need to ask what does this data mean to me, and then explain what that meaning is and why I find it meaning that – I don’t need to be deheartened because I don’t see the meaning that others see.

    Now, I just need to figure out – what is my meaning – when I find themes and subthemes, I need to ask the question – what does this theme mean to me? Not what does this theme mean in general. However, I need to write it as if I’m answering the question “what does this mean (in general)” – because I’m writing the results of something that is supposed to be some form of “this is what I found, this is what it means” … and the formalized research report format leaves out the “to me” in the way it is written (and hence leads people to believe the data is less biased then it really is) … but that is another issue … so my next step is asking, what does this mean … and being OK if it means less or different things to me then it does to others who are reading my dissertation … because, the goal is my meaning making …


  • Why I dislike rubrics in my classes

    I teach in a M.Ed. in Instructional Design program, where my students are generally mid-career professionals. They are all in the program because they want to gain skills that will help them make the career transition to instructional design – or enhance their abilities in the current careers. Either way, they come to class motivated.

    One area where I sometimes get comments from my students is the lack of rubrics for my courses. In the context of the courses that I’m teaching, I hate rubrics. Rubrics are all about my expectations of students and not about the students’ potential. They in no way take into consideration the individual talents of my students, what each brings to the course, and they pre-judge what I think will be good work.

    They change the behavior of students – causing them to focus on what is necessary to ‘make the grade’, rather than the internal motivation of excellence for excellence sake. They also take away an aspect of learner creativity – as the students then focus their assignments on meeting the rubric requirements rather than on making an excellent product out of their projects.

    I always worry when I provide too much guidance in assignments. I worry that by providing that specific guidance I take away learner agency. I make the learning about what I, as the teacher, want, and not about what the learners themselves want.

    Instead of rubrics, I have opted for checklists. I provide a checklist of what things need to have, and then I encourage students to be creative in how they solve the problem. I also give them permission to not be perfect, and not necessarily be ‘successful’, because you cannot be innovative if you have to be successful. The requirement to always be ‘perfect’ is one which causes students to be overly cautious in their work – and means they shy away from trying new things and opt for reproducing things they already know.

    I am lucky that I don’t need to ‘rank’ my students. My students do not need to be compared to one another. I don’t need to grade on a curve. My goal is to get all my students to grow in the class – for all of them to be challenged and to overcome the challenge – to prove to themselves that they can do it.

    My teaching is much less about what my expectations of my students are – and more about helping my students overcome their own expectations of themselves. Personally, I think a rubric would get in the way.

    What do you think? Do you use rubrics? How do they help? How do they hinder?

  • Complexity, Complicated and Health Science

    One of the challenges I find with health science is that it assumes that health and the human body is something that is complicated, but not something that is complex.

    What I mean by this is a concept that is explained by Davis and Sumara (1997), where they describe how “complexity theory draw a distinction between the descriptors complicated and complex” (p.117). Complicated systems are described as systems that can be understood by analyzing the individual components and adding the components together where, complex systems are more than the sum of their parts, in that they cannot be understood by breaking them apart.

    The premise of the scientific method, however, is based upon controlling certain variables and altering other variables. The idea is that if you hold certain parts fixed, and move the other parts, then the change in result is directly because of the change in the moving parts. This makes complete sense when you are looking at complicated systems, however, it does not make sense when you are looking at complex systems.

    One flaw with the health research is the primacy placed on scientific method as if it were the only way of knowing – but also as if the systems being studied were merely complicated systems, instead of complex ones. Maybe this means that we need to start thinking about ways in which to study the human body, disease, etc, in the ways that complexity theorists use rather than through the lens of scientific theories.

    What do you think?


    Reference:

    Davis, B., & Sumara, D. J. (1997). Cognition, Complexity, and Teacher Education. Harvard Educational Review, 67(1), 105-125.


  • breast cancer bootcamp

    At the BCC annual conference yesterday, one of the speakers, Dr. David Spiegel, mentioned that patients have much less anxiety if they take time at the beginning to make informed treatment decisions. One of the challenges that we run into when we are told we have cancer is the desire / fear / need to do something about it quickly. IMHO, the early detection rhetoric helps increase this need to do something about it quickly. The message we receive is that if you cancer you need to rush into treatment. However, this is not always the best course of action.

    Note, that I’m not an oncologist or cancer doctor. There are some cases where that rush is indicated, but in many cases, the cancer does not grow so fast that waiting a week or two will have a dramatic impact. Often you end up waiting that week or two anyways – while you wait for detailed pathology results, various scan results, maybe even genetic test results, and insurance approvals (yes that too is part of the process).

    There is a time in that window where patients could do some kind of educational intervention that helps them learn to make more informed decisions, and make decision based upon their personal values, rather than being forced into decision that doctors make for the patient – doctors who often just met the patient and are making decision based upon disease characteristics alone, rather than a combination of disease characteristics and patients longer term life and health goals.

    This got me thinking – wouldn’t it be nice to have some form of cancer boot camp – where once you are told you have cancer, while you wait for appointments and test results, that you could do some of that important identity and values work, as well as gain some knowledge about the disease itself, that would help you make better treatment decisions – better decisions that will help you with longer term happiness?

    When I talk to other survivors about things they wished they knew and understood, I often here things like – I wish I understood that I had choices. I wish I understood that I didn’t need to urgent jump to treatment, that I had even a little bit of time to think through things. I wish I understood some of the true long term impacts of the decisions I was making. I wish I understood some of the side effects better. I wish I understood that sometimes choosing a doctor is about figuring out who you have chemistry with, not necessary who is ‘best rated’.

    There are so many different aspects that are address a little in support groups, but a lot that is not. And support groups are often short duration – 90-minutes once a week or once a month. Wouldn’t it be nice if in that crazy time before you have a solid treatment plan, that there was some kind of experience – a mix of educational, emotional, and spiritual – to help you better deal with the diagnosis and make better decisions? Wouldn’t think help you live better with those decisions?

    I found myself thinking that this is the type of work I’d like to be doing. I’d like to be helping coach women through that process. One of the challenges is that women rarely make it to support organizations, like BCC, when they are in that state. They usually do exactly what they are told by the first doctor they see because of fear – because the rhetoric says that early detection (and therefore quick treatment) saves lives. They end up in support groups after all that has already happened – after critical decisions have already been made – and after they find themselves struggling to live with those decisions or find themselves wishing they were given more options. But in order to get that education (or boot camp) to happen sooner in the process, the diagnosing physicians need to buy into the need for it. They need to be willing to address the fact that they, the diagnosing physicians, are not necessarily the best person to be making these life altering decisions (their job is to outline options, and provide recommendations, but not make the decisions – they are not the ones who need to live with the decisions). In the new world of medicine, where patients have access to information but also to each other through support groups and social media platforms, physicians need to learn ways to ceed control, and support providing patients with the right tools to help the patient make the right decision for the patient – the decision that will lead to longer term acceptance of the situation.

    What do you think of the idea of a breast cancer bootcamp for newly diagnosed? Would it be something that could work in an online format? What type of information and what type of reflection activities would you think would be of value? If you have breast cancer, what did you wish you knew before you began treatment?

  • Critical health literacy, statistics, and treatment decisions

    I was asked to choose between ACT chemotherapy and TC chemotherapy. Both were shown to be as effective, so the decision was mine. In making the decision, I looked at the potential side effects of each, as well as what the standard of care would be in Canada. Further, I looked at the literature and saw that there was more data on the ACT regime. I used that information together with knowledge of how my body reacts to things and my gut-feelings to decide on the ACT chemotherapy. The medical oncologist confirmed my decision by saying that 80% of women who need chemotherapy for hormone positive breast cancer get ACT chemo.

    Now that I am much further out from the decision, I can see the problem with this statistic and some of the other data I used to make the decision. At the time, I felt comforted by knowing that this was a chemotherapy regime that was used in other places, and that it was common. If 80% of others were getting it, then it had to be the best choice right?

    The problem is that the statistic is skewed by time. The longer a treatment is available, the higher the statistic will be. In addition, the longer a treatment option is available the more 5 year and long-term survival data there is (academic measures of treatment used in evidence-based medicine). Once a treatment becomes standard of care internationally, the number of people that get that treatment becomes much higher than other options. It means that newer treatments will always have lower numbers – at least until they are proven to be more effective and take over as standard of care. So, the percentage of other people who have had that treatment isn’t necessarily a useful number when it is used to make the treatment decision. Further, the older a treatment is, the more likely there is long-term survival data on that treatment. It doesn’t mean the treatment is better, it just means there is more data about it!

    I also did not appreciate that looking to the standard of care decision was also not the best information for making my decision. It was comforting to know, but I didn’t appreciate that newer treatments take time to become the standard of care. So the newer treatment might actually be a better choice, but the statistics and standard of care data are not data that would support choosing the newer treatment options.

    This is one place where the practice of “evidence-based medicine” can fall apart when it comes to decisions in care. The evidence will almost always suggest the older treatment options. There is a bias towards the older and better understood option. That is a nuance that was not appreciated by me, an academic, when I was in the position to have to make the treatment decision. It was not something that anyone pointed out to me.

    I think this might also be an important factor when promoting clinical trials. In order to advance care, clinical trials are important, and often provide better treatment options – or at least that is their goal. However, patients can shy away from them in part because of a misunderstanding of the data, and not appreciating the biases associated with the current standard of care.

    Another non-medical place where I see this bias is on YouTube – I have been using YouTube for years to provide how-to tutorials for technology. My most viewed video is an old one. But because it has been there for years, it has a much higher view count than newer and better versions of the same tutorial. The higher hit count of the older one causes more people to watch the older one, which in turn increases the hit count more. The newer one cannot catch up. There is a bias towards the older one because it has a history. It has been available longer and therefore has had more time to get hits. I see this bias all over the internet. Whenever an already known entity needs to compete with something new – the older known entity goes into the competition with a bias because of its history.

    I think this is another way in which we can look at health literacy from a critical perspective – what are the biases in the data itself?

  • Is it critical if you don’t also question the value?

    Thanks to Marie’s weekly round-up, I was lead to a post on Critical Health Literacy by the Breast Cancer Consortium. Initially, I really liked that they were tackling the idea of critical health literacy, but then as I read through the post I felt like something was off. I realized that they were defining critical in a narrow way. They linked critical health literacy directly with evidence medicine and a need for patients to understand the ways evidence-based medicine works in order to help patients make healthcare decisions. Sounds fine, except …

    The word ‘critical’ has a completely different meaning when taken in the context of social science. It isn’t about evaluating sources for their scientific merits, rather it is about critically examining sources to appreciate the biases that go into the sources – and this critical examination includes examining the biases that go into the scientific-based sources.

    Philosophically, the scientific worldview is that there is a one truth – and that it is possible to do science in an unbiased way, where in critical theory there is an appreciation that there is no such thing as unbiased. It is impossible to do things without bias, as each thing we do involves so many individual decisions, that you cannot completely remove bias.

    I’m challenged also by the different value systems at play here. One of the value systems that I am constantly fighting is the view that scientific knowledge is more value than non-scientific knowledge – you see this in medical research when you hear things like how randomized control trials (RCT) are the gold-standard. It puts a value for that type of knowledge generation which doesn’t necessarily apply to all situations. It doesn’t account for the complexity or variability of human bodies. Even in a RCT, someone gets to decide what variables are being measured. Someone gets to decided what it means to be successful. Those decisions impact the inherent biases in the RCT results.

    The scientific method attempts to take the human element out of the equation, and yet, when we are dealing with healthcare is it all about the human element. So, a narrow definition of critical health literacy that privileges scientific knowledge without questioning it, is a definition that is fundamentally missing the critical worldview.

    I think health literacy needs to look beyond what science has to offer, and needs also to look at what other social sciences and humanities can offer – health literacy should be looking at ways to improve the human condition, not just to improve some criteria that some group of people (e.g. physicians, researchers) deem to be important.

    What I’m calling for is a critical look at critical health literacy!

  • Health literacy as a patients job

    An article on Simplifying patient communication can lead to better health outcomes by Eve Becker, crossed my stream today. I was struck by this statement:

    “Enter the field of health literacy, which aims to help physicians increase patient communication, speak in plain language and write clear prescriptions with easy-to-understand instructions.”

    I found myself wondering why the field of health literacy was defined by something physicians need to, rather than something that needs a more systematic approach. I don’t think of health literacy as a physicians job, I think of it as a patients job.

    I also wonder, why don’t we teach health literacy in school? At one point or another, everyone will get a prescription from a doctor. Why don’t we teach, in health class, how to fill a prescription and what the different directions might mean?

    Patient with chronic or critical illness have special health literacy needs. Their interactions with the healthcare system are much more complex. These patients need to develop a special type of health literacy. This is what I’m trying to figure out with my dissertation. What are the things that patients of critical/chronic illness need to learn, and how do they go about it? I do not see health literacy as a physicians job, I see it as a patients.

  • Blogs, Bikes, and Breast Cancer

    Many of my readers know that in a previous life – 9 years ago now – my husband and I took 16-months off and road our bikes around the world. It was this adventure where I started to blog seriously for the first time. It is also where the domain name Going East came from – we left from Ottawa and went east until we got back home – hence going east.

    In addition to blogging, I also started following blogs. I read them obsessively to help prepare for the trip and during our trip. We had guidebooks and maps for the places we visited, but they were of limited use. Guidebooks were often years out of date and not bicycle touring specific. Maps showed major roads, but not the good roads for cycling. When crossing international borders, we also needed to know what the current visa situation was – something that guidebooks cannot keep up with, and even government websites aren’t always current. We did, however, find that we could following bloggers who were a few weeks ahead of us, following a similar path, and use their experience as a way to help guide us. The information they provided was both bicycle touring specific and current. In addition, we could reach out to those who were a couple weeks ahead of us and ask them specific questions. They often were happy to share their experiences, and if our paths crossed we even met up in person.

    It occurred to me that this is very much like academic literature and blogs for breast cancer treatment. The academic literature is well researched, but also years old (it takes years to get published) and only provides the perspective that the scientists/clinicians care about, not the information that patients care about. The academic literature is the ‘guidebook’ for breast cancer. Where breast cancer blogs, and other social media, provide more specific information, and often more current information. They share what the patient is experiencing, often as they are experiencing it. In addition, many breast cancer bloggers are happy to share their experience with anyone who sends them a note. I know that I am. I know that several of the bloggers who I follow were happy to talk to me when I needed it.

    My point is that guidebooks and academic literature provided well researched information that is of general interest to a target audience. The cycle tourist and patient experiences are specific audiences that are not the target of guidebooks and academic literature. If you want more current information, and you want more specific information, then blogs (and other social media like Twitter chats and Facebook Groups) can fill that gap. It is not just that social media help provide information and context on what it means to actually live with illness, it is also that they provide more current information and information that is of specific interest to patients.

  • Empathy and suffering #digped

    Before vacation I attended digital pedagogy lab institute (DPLI) in Fredericksburg Virginia. I haven’t been able to write a summary blog post for the experience. It was not at all what I was expecting. I was thrilled to spend a week with Maha Bali and Kate Bowles, so really, I did not enter with any expectations other than to share the space with a couple of my favourite people. Since I was attending the networks track, I did hope to meet some new people and make some new connections/friends.

    One of the ah-ha moments that did occur was when we were having a discussion around empathy. I shared that after my cancer diagnosis my empathy level for others significantly expanded. I found that it was my worry about my loved ones that made me sad. I could feel the pain they were in because of my diagnosis. It was heart wrenching.

    It was in this discussion that I drew the connection between suffering and empathy. Because I was suffering, I felt increased empathy towards others. To me, this explains the high empathy levels in some of my friends – because I know they are suffering, and that personal suffering translates to increased empathy for others.

    I think that is one of my big take aways from my experience at DPLI.

    It leaves me with the question, can you be deeply empathetic if you have not had personal suffering?

  • Verisimilitude at #digped

    Validity “means that a work seeks verisimilitude; it evokes in readers a feeling that the experience described is lifelike, believable, and possible, a feeling that what has been represented could be true” (Ellis, Adams, & Bochner, 2011, p.284)

    “Lie down on the bed, chest down with your breasts in the holes, hands above your head” the MRI technician says to me, with a caring inflection in his voice.

    I follow the directions of the MRI tech. I can feel the IV in my arm tug a little as I hop onto the cold bed and position myself. Lying on my stomach with my breasts sticking down through the holes. I find myself thinking about how surreal this entire experience is. The MRI tech places earphones on my head and asks “are you comfortable”? I wouldn’t exactly call this position comfortable, but I can manage it.

    “I’ll be just on the other side of the glass. Squeeze the ball of you need out of the machine. I will talk to you throughout the scan. OK?” he asks as he prepares to leave the room and begin collecting the images that will help determine the extent of my cancer.

    I feel my elbows bumping up against the sides as the bed slowly moves into the MRI machine. I am surprised by just how small it is. I’m thankful that I’m looking down and not up, so that I don’t feel that my world is collapsing in on me. I take a deep breath.

    “The first scan will be two minutes”, I hear him say through the MRI speakers. Then it begins. A whirring that reminds me of passing fire trucks, following by clicking and shaking. Whirs, honks, and other sounds that remind me of the sounds of the alarms and shakes of the first container ship we travelled on back in 2008. I’m transported to the Bahamas, watching as the cranes that remind of me of the four legged creatures in Star Wars load and stack containers, shaking the entire ship when the large deck covers are put in place. I am brought back to reality when the tech says “we are going to put the contrast now, you will feel a warm sensation. The next scan will be 5 minutes”.

    Yesterday, I gave a brief (about 8 minute) presentation at Digital Pedagogy Lab Institute (DPLI) about my dissertation research. As part of the presentation I told two short stories – the second one is what I shared above.

    After the presentation, I had several people talk to me at different times. One person mentioned that listening to my story about the MRI brought back memories of a time her son had to have an MRI. Another person shared that her sister was a breast cancer survivor, and that some of what I talk about really resonated with her.

    In my dissertation work, when I step up to the front of the room and read my stories, I am struck by how people come to me afterwards and tell me how the stories resonated with some aspect of their lives. This is what I believe Ellis, Adams, & Bochner mean when they speak of verisimilitude.

    During out track at DPLI, we have talked about how each person hears the story in a different way. Personally, I find it particularly rewarding to have those quiet conversations afterward, when someone tells me what they heard when I told my story. That is the validity in the research that I do.

    Mostly, my goal in writing this post is to share and say thank-you to those who have told me how my work has resonated with them.

    Does this story resonate with you? I’d love to hear your story. 

    Feature image: Public domain

  • Qualitative researchers – interrater reliability help wanted

    Friends, I’m looking for a few people family with qualitative research coding to do some interrater reliability for my dissertation. What this would involve is coding approximate 30 blog posts (links provided to specific posts) based upon the themes that I have identified, followed by a conversation with me about your rating experience. If you are interested, please pop me an email or respond to this post. Thanks, Rebecca.

  • Survivor of the journey

    I struggle a little with my choice of words – in part because others are so challenged by it. I’ve talked about the battle metaphor and my challenge it with. Now I find myself reflecting on the words Survivor and Journey.

    I chose to identify as a breast cancer survivor. I use the term survivor for lack of a better word. It is the word the most people understand. It doesn’t feel authentic for me because I will not know if I survived breast cancer until I die of something else. It is also a word that is hurtful to dear friends of mine – those with metastatic breast cancer who are living today but know that they will not survive breast cancer. For them, the disease is terminal. I have an internal struggle when I use that word, but alas, I use it because it is a term that other people understand.

    Journey is another one of those words. Every time I write the word journey I think of Emily McDowell’s empathy care “Illness is not a Journey”. And she is right, illness is an experience. Calling it a journey puts some pressure for the need for personal growth. Sure, some people do grow, and have spiritual awakenings as a result of their cancer experience, but not everyone does, and no survivor should be expected to have a magical transformation.

    But then I am stuck for another word. I don’t have a better option to explain my experience – especially when I’m writing it in the form of an autoethnography, where there is specific insight and knowledge coming from the articulation of the experience. A journey is to travel from one place to another. For me, the experience of breast cancer was a journey – a form of transformation. From a purely academic perspective, I see that I have transformed (maybe grown). I see value in different types of research. Would that have happened without the cancer experience? Maybe, but likely not to the same extent that it has.

    The interesting thing is that with time I will learn to own the words the I chose. I have learned to own it when I call myself a survivor. I just haven’t yet chosen to own the word journey.

    What do you call your experience with illness? Do you like or dislike the word journey?

  • Care perspective versus Illness perspective

    I have been thinking a lot lately about perspectives – struggling really – trying to figure out where my thoughts and ideas fit within the systems that I’m studying.

    One challenge that I kept running into was that I am reading (literature reviewing) a lot of information provided from a care perspective – that is from the perspective of providing healthcare. There is a lot of medical literature on how to provide better care or improve population health – and how health literacy is an issue especially for population health problems. But that isn’t the perspective that I’m studying. I am not a healthcare professional, nor a health science or population health professional. That isn’t the perspective I want to study.

    I was reading Kleinman (1992) where he mentions of difference of ethnographies as being of illness or care. That made me realize that the perspective that I am seeking is that of illness not the perspective of care. Further, when looking at patient experience literature, I found different perspectives – with different purposes – such as the administration of health care looking at cumulative data around patient experience in order to improve processes and policies related to the delivery of healthcare. Then there are clinicians who look to improve the experience of individual patients and improving “outcomes”. But the perspective that resonated more with me is that of the social scientist that looks at the experience of illness in the broader context.

    It is with this broader illness perspective that it occurs to me that an ill person is only a patient in the context of interactions with the healthcare system. Beyond the bounds of the healthcare system, they are a person with illness or an ill person. They are not a patient. The scope of what I’m looking at is of illness experience. I’m in not necessarily trying to change the care experience of others, however, I do hope that my research helps improve the illness experience.

  • Not fighting a battle – the closure to the narrative is death itself

    Recently, I read a book chapter by Arthur Frank (2009) titled “The necessity and dangers of illness narratives, especially at the end of life”. It got me thinking.

    One of the pet peeves among many cancer bloggers as well as those with metastatic breast cancer is cancer as a war metaphor – that is, the fighting a battle with cancer language. Many people don’t like suggestion that those who died from breast cancer “lost”, as if they did not try hard enough, as if breast cancer was something that involved winners and losers.

    In the article Frank says that “narrative thinking embeds the idea that obstacles must be overcome for there to be a closure. Moreover, obstacles are necessarily understood as a personal test, conveying a sense of individual victory or defeat.”

    If I look back on my experience, there was a time where I identified as a warrior. The metaphor worked. I was in chemotherapy and suffering from a variety of side effects. I needed to fight to keep exercising and do my best to keep strong. The war metaphor worked for me. It motivated me. In reflection, I see that it worked because I needed the sense of closure. I needed to know that the immediate experience I was having would end. To mentally make it through all the suckiness that was chemotherapy and then surgery recovery, I needed a sense of ending. So the war metaphor gave me a sense that there would be closure to that part of my life’s narrative.

    But now, after acute treatment for early stage breast cancer, I feel that the war metaphor no longer works. It doesn’t work for my friends who are metastatic and will die from this disease. But it also doesn’t work for me. With survivorship, one of the things I am coming to terms with is that there is no sense of closure. There is no clear ending. The war metaphor no longer works for me. I’m living with all the side effects of treatment, and with all the fears of the cancer coming back, or another cancer happening. I do not expect that there will ever be that pretty closure that narratives seek. But I also think that is part of the point.

    It got me thinking about why the war metaphor works for some people. With the war metaphor there is an a sense of ending, a sense of closure. But for most people with breast cancer, the only ending or sense of closure is death. It is not a narrative that is meant to have closure. The need for closure takes away an aspect of the experience that is paramount to those who are surviving after breast cancer treatment. You don’t know that you “survived” breast cancer until you die from something else. And those who do die from breast cancer, don’t lose a battle, they die. The sense of closure in the narrative is death. It doesn’t need to be a battle lost. It shouldn’t be a battle lost.

  • Giving voice and face to the illness experience

    The other day I had the opportunity to have a conversation with the lovely Bonni Stachowiak for her podcast Teaching in Higher Ed. In the podcast, I talk about my experience with the intersectional identity of educational researcher, blogger, and breast cancer patient.

    You can download and listen to the podcast from this link: http://teachinginhighered.com/podcast/giving-voice-face-illness-experience/.

  • Remission society and mourning my fantasy future

    I apologies to those who read all my blogs, as I am cross posting this. I’d love to hear answers from the various readers of my different blogs.

    I want to connect two ideas: the idea of remission society as described by Arthur Frank (1995), and the concept of the fantasy future that I learned while on a cancer care retreat at Commonweal (February 2016).

    Frank (1995) explains that anyone with a chronic illness lives in the remission society. Frank (1995) describes how “in modernist thought people are well or sick. Sickness and wellness shift definitively as to which is foreground and which is background at any given moment. In the remission society the foreground and background of sickness and health constantly shade into each other” (p.9). I interpret this as the way in which I shall never not be a cancer survivor. Breast cancer is a sickness that will always be part of my identity, regardless of how healthy I am at any given moment. It also will always affect my wellness. I will never be well in the same way I was well before cancer. I may be in remission, where I am not sick but nor am I well. I think of remission as this space in-between, or perhaps above or below, not on the same axis as the well or sick dichotomy.

    In order to deal with my emotional wellness, I needed to address the loss of my place in the well category in the well or sick dichotomy. While in active treatment, I was clearly in the sick category; however, once chemotherapy and surgery where done, and the last of the known cancer was removed from my body, I was no longer in the sick category, but also was not in the well category. I was in remission. It was learning of the falseness of this dichotomy that helped me move beyond it. During a group therapy session, the therapist made a reference to the idea of a fantasy future. That is, the concept that all futures are a form of fantasy. We imagine what our future life might entail (e.g. growing old together, remaining in perfect health), but the reality of life is never what we had imagined. A big part of my emotional healing was to forgive my body for the loss of my fantasy future.

    Another part of this reality, and one that I’m still working on, is that it should help me focus more on the present. What is in the now, and the short term future, rather than the long term future. This is, in theory, to help reduce anxiety today, but focusing on today rather than focusing on the uncertainties of tomorrow. However, this of course causes the problem I describe in my paradoxical future. Where I struggle with the challenging balance between planning for the future and seizing the day.

    Perhaps that is in part what it means to be in the remission society (as opposed to being sick)? When I was clearly sick, my focus was on a very short timespan. I saw life on very short horizons – tomorrow, next week, next month – never more than three months. I just couldn’t plan that far in advance. But now, after I have mostly healed from chemotherapy and surgery (I say mostly, because some of the damage will never be healed), I see the potential for those horizons. It is because I see them only as potential and not concrete that I run into the paradox. Sure anyone who is well will say that they don’t see the future in concrete terms, but in the scale between potential and concrete, a well person sees the future a lot more concretely and someone who is sick, who only has a sense of potential for the future. In this world of remission society, I’m somewhere in the paradoxical middle. Afraid to have a fantasy future, because I got burned by that idea.

    Do you have a fantasy future? How concrete is your sense of future?

    Feature image CC0 via MaxPixel.

  • Closed open research

    I find it odd/annoying when I’m asked to participate in a research study about open practice, then the consent form for the study says that all identifying information will be removed and my contribution will be anonymous. To me this is a huge contradiction. The study is looking at practices that I do in the open, and yet my participation in the study itself is not allowed to be open.

    Sure, some participants in the study may want to be anonymous, but as a participant shouldn’t I be the one that makes that choice? If anonymity does not affect the study itself (that is, there is no harm in identification, and no risk that my self-disclosing causes the identification of someone else that doesn’t self-disclose), then I should be given the choice. It should not be required that I not be identified.

    The internet and participation in open practices is making this issue more poignant. I want to shout out to all IRBs and researchers: Your research participants should be given the  choice of how they are identified in your research. You may actually be doing more harm by not identifying your participants – as you are taking their words and ideas and melding them into your research and not attributing them to the participants themselves. If there is no harm to other research participants, there is no reason to require that I not be identified.

    So, yes, I’m happy to participate in the study, but I am the one that gets to choose how my words are attributed.

  • Why I’m changing my license to CC-BY

    For a long time now I’ve debated how to license my blog. Originally, I don’t say anything, which means it was copyrighted. Then I made the copyright explicit.

    At one point, and article that I co-authored was included in a compilation book after it had been published in a journal. We asked the journal about it, and the said that the journal has an open license (CC-BY), so people are welcome to take articles and republish them as long as they included the author attributions. They were not required to even mention the journal. We didn’t like the idea that someone else was profiting from our work. It seemed unfair. This is part of what made me want to keep my blog as copyrighted material.

    A few weeks ago, Robin DeRosa was a guest in my class. She inspired me to think again about my licensing. I’m not exactly sure what she said, but it inspired me to rethink my choice of licensing.

    Then a post from a friend, Maha Bali, was picked up and republished on the Huffington Post blog. She wasn’t immediately aware of it because it was originally published elsewhere with a CC-BY license. The republishing on the Huffington Post blog meant that a lot more people heard her voice. Her very important message was rebroadcast, which meant a lot more people read it.

    That got me thinking a lot more about this blog and all my other blogs. I realized that for this blog, there isn’t really anything that I would want to use commercially, but also, in the academic world it is much more about the prestige economy – by that I mean that getting my name out there will be more valuable than keeping any particular blog post. By allowing people to copy with attribution, I am encouraging the the re-use of content on my site. By stating that I want attribution helps with getting my name out there; therefore, a CC-BY (creative commons with attribution) license makes more sense than copyrighting.

    Now for my other blogs, I don’t know yet. I have left them all with copyright for now. I’m a little concerned because at least one researcher reported that they did not use any copyrighted blogs as research data – I thought that was a misinterpretation of copyright – but it concerns me that my blog might get excluded from research because of the copyright. Note that I make an explicit comment about the use of my breast cancer blog in the About page for that blog.

    Why do you CC or not CC your blog?


  • Paradox of Patient Empowerment and Care

    I find myself looking at all my past experience, and making connections between what I know as an educator, and PhD student, to what I have experienced as a patient with critical/chronic illness. Leading off from Autumm Caines’ post about Virtually Connecting focus groups, I want to chat a little more about the paradox of patient empowerment and care. I watched the first focus group and attended the second and third. It was during the third focus group that I was challenged on using a famous Audre Lorde quote “you cannot dismantle the master’s house with the master’s tools” – that challenge led to an ah-ha moment for me – the paradox of patient empowerment and care.

    When we talk about the need to empower patients, we talk about patients taking an active role in their healthcare. This is a challenge the often very paternalistic healthcare system – where we as patients are suppose to do what we are told. The language often used is that of “compliance”. It goes further to sometimes even blame the patient. We hear things like “the patient failed to respond to this medication”, rather than “the medication failed the patient”. Language matters.

    In one breath, I see patient empowerment as giving patients a larger voice in the healthcare system. I talk about medicine being practiced with patients rather than on patients.

    On a side note, I wonder how much of this is an American view point – where here you often (if you live in a populated area and have the privilege of good health insurance) get to choose who provides your healthcare? This is the land of second and sometimes even third opinions – but it is also the land of shopping for healthcare providers that align with your needs/personality, etc. The choice of provider affects the culture. I do think the empowerment situation is somewhat different in a socialized system, where you don’t have the choices in who you see (at least not to the same extent). In Canada, the gatekeeper is your family medicine physician (primary care physician or PCP). When you need a specialist, you go through your PCP. In the US, at least from my experience, your insurance company plays a much larger role of gatekeeper. Your insurance company determines if your PCP needs to make a referral or if you can self-refer. Your insurance company (and bank account) determine which providers are in-network – and which ones you can afford to see. In many cases, self-referral is what happens. When I was diagnosed with cancer, once I had a confirmed pathology, I could self-refer to any surgeon or oncologist. I didn’t need my PCP to make the referral.

    Where do I see the paradox? I see it in the need for the healthcare system to provide care. When you are in the middle of a health crisis, you need to know that the healthcare system is going to care for you. You need the maternalistic sense that someone(s) has your best interests in mind, and that they will ensure you are cared for. When you are in crisis, you don’t need, nor do you really want empowerment. You need care.

    Going back to the Audre Lorde quote “you cannot dismantle the master’s house with the master’s tools”, the patient empowerment movement isn’t so much about dismantling the tools completely, although it is about dismantling some of the paternalistic tendencies in the system. There are times when we need the use of the master’s tools. We need the expertise of our physicians and other allied health professionals. We rely on them for care. But when we are not in crisis, we also need to know that our voices are heard.

    In online teaching, we talk about the transition of teacher from “sage on the stage” to “guide on the side”. In many ways, this is the transition that empowered patients are looking for in healthcare. They want their physicians to be guides rather than sages. The expertise is desired, but also the recognition that patients carry prior knowledge and expertise. I like to use the phrase “I am an expert in my body”. My medical oncologist is an expert in breast cancer and the pharmaceutical treatments for it, but he is not an expert in my body. I am the one that is living in it.

    Do you see a paradox between patient empowerment and care? How is patient empowerment different in socialized medicine settings? 

  • Intersectionality, Identity, and Health Humanities #healthhum2017

    The last couple of days I’ve been attending the Health Humanities Consortium conference in Houston Texas. The experience has been rather mixed for me, causing me to reflect on so many different things. One of the themes of the conferences was that of intersectionality. The idea that we all carry a variety of identities, and it is sometimes the combination that makes our experience important/special/unique.
    It is my intersectionality that makes the sharing of my experience valuable. In part because my privilege and my abilities allow me the voice to share my story. I need to own my own identity. I’m a white, hetero, ’new’ scholar, Canadian, California resident, female, ‘young’ breast cancer survivor and someone with celiac disease …. and much more. Each of these things played into my experience at the conference.
    I found myself challenged as someone who came to this conference not knowing anyone – new to this community and the scholarship of this community. My initial attempts to interact with people didn’t feel well received/reciprocated and this took a lot of energy from me. Something that I’m realizing that I have a lot less of post-cancer treatment.
    I found myself as an expert from the ePatient experience – annoyed when I heard the rhetoric of “everyone is a patient” as those of us dealing with critical and/or chronic illness can attest that our experiences as patients in the healthcare system are dramatically different than those who experience temporary illness.
    When I heard about medical humanities programs I found myself wondering if there was room for an ePatient stream. What do I mean by that? I mean that I don’t see a clear place for peer-to-peer patient experience, nor patient advocacy within health sciences. I see a need for an ePatient track – where ‘insiders’ have a space to explore their experience in an academic setting. I think health humanities might be the right place to place that type of exploration.
    I find it interesting that it has never occurred to me that perhaps disability studies is the home for this type of work. I have never related to it, until I started typing this it had not occurred to me that there might be a place there. That being said, I don’t necessarily think of critical and/or chronic illness as disability. I feel there is a difference, but cannot figure out how to articulate it. Perhaps it is because I don’t think of my chronic illness as a disability (although technically both cancer and celiac are legally considered ‘disabilities’).
    I found myself thinking, wouldn’t it be nice to see more ePatient academics presenting, or even ePatients who are not academics, to help balance the outsider perspective that is prevalent in the scholarly spaces. The problem is, those who are insiders aren’t necessarily willing to share their insider experience – especially in health fields where the predominant line of research asks that we be ‘objective’, denying our personal relationships to the discourse.
    I found myself challenged by the food – or lack their of. I’m a celiac. It means I need a strict gluten free diet. The organizers did a great job of setting aside a special lunch for me, so that I had an option. The problem is, special often gets lumped together. I’m not sure if this is a caterer problem or a conference organizer problem. I am not a vegan. I need protein. I also don’t eat soy. I really really don’t like it when I get gluten-free bread in my GF meal. Why? Because I cannot tell – it is too easy for the GF bread to get switched for a non-GF bread. I really want a GF meal that LOOKS like a GF meal, one that has protein, and one that I can trust. The is hard when you are attending a conference that is out of town. It hard when there aren’t a lot of options that are within walking distance of the conference. It is an invisible disability. Dealing with food takes a LOT of extra energy.
    At times, I found myself challenged as both a novice and an expert at the same time. I didn’t know where or how I might fit within this community – and yet I found the presentations I attended all captivating. I found myself relating more when then speaker quoted the seminal characters in education and critical theory – in part because I have some background there. I struggled more when the links where to literature, having never taking a lit course!
    My thoughts came full circle today when I attended a session today where several scholars talked about teaching using Audre Lorde’s The Cancer Journals. I’ve been thinking of writing a piece that juxtaposes her diaries with my experience. When the first scholar talked, I found that I was questioning myself. Who was I, someone who did not share her intersectional identity, to compare my experience to hers? Why would I have the right to do so? But then I thought, I’m allowed to have my experience. My intention with such a paper is to describe both the differences and similarities to our experiences. I think the exercise will be useful, even if it doesn’t result in a paper.
    Although I had a mixed experience with this conference, I do plan on attending next year, largely because it is at Stanford – which means I don’t need to travel. It means that I can sleep at home, but also that I can easily pack my own meals. Having more energy to experience the conference itself, rather than dealing with all the energy (and pocket book) sapping issues associated with conference travel.
    I’ll be thinking a lot more about this experience and my intersectionality as I consider where I might end up when I finish my PhD.
  • Living Pathology – an Open dissertation blog

    I have decided to brush off the domain I had originally setup for my dissertation. I have much better sense of where the project is going – so I’m using that blog as a way to share my writing as I write, and my field notes and ideas as they occur to me. It is a living blog.

    David Elpern at http://pathography.blogspot.com/ defines pathography as “a narrative that gives voice and face to the illness experience. It puts the person behind the disease in the forefront and as such is a great learning opportunity for all care givers and fellow sufferers.” I chose Living Pathography for the domain name because all the current work on pathography relates to books rather than blogs. I think of blogs as living books – ones that can be updated regularly – but also ones that contain reflections of the experience as it is happening, rather than the post-processed reflective version that is presented in book form. There are less constraints when blogging, allowing the writer to express illness in a raw and authentic way, which provides a layer of learning that can be lost when the experience is distilled into a book narrative.

    I will cross post things here that may be of interest, but also, there are things that happen on this blog that are completely unrelated to my dissertation (e.g. Virtually Connecting and Virtually Connecting ePatients). The new site will focus on my dissertation as well as other academic papers, conference presentation, or book chapters associated with health blogging.

    If you are interested in following specifically my dissertation journey, I invite you to follow me at http://livingpathography.org or on Facebook at: https://www.facebook.com/livingpathography/

  • Identity

    As part of the PhD process, I’ve been reading through my blog from the beginning. I wrote it, but I have never actually read it – at least not in this way.

    I am immediately struck by how my memory of the time doesn’t completely align with what I wrote. I know that what I wrote was a much more accurate reflection of what I was thinking than my memory of that time. There are a few places where I realize that what I wrote doesn’t even begin to capture what I was feeling – I can tell when I was holding back to help protect family members who were reading – but there were many times where I was fearful, in pain, and honest about it – that I don’t actually remember – at least until I read about it.

    I’ve also been struck by how well I managed to write through (and see) brain fog. Now I know there are additional brain fog moments – which I haven’t gotten to year – but certainly the early days of taxol, and the cognitive challenges I was facing – I wrote about in some detail. I will write more about this later, once I’ve read more, as I know that my cognitive issues continued for much longer than I realized.

    One of the themes of my posts have been my exploration around identity. Heck, the subtext of this site is “I never thought I’d want to identify as a breast cancer survivor”. I was deep into exploration of my identity when I got diagnosed, so it was definitely something that was on the forefront of my mind when I started this blog. What I find interesting now is that the things I was worried about then no longer worry me. I care a lot less about what other people think of me. I’d be naive to say I didn’t care, just that opinions of others are generally less of a concern to me now. It is less of a reason for me making the decisions that I do.

    I also wrote a lot about body image. I wrote about my concerns as I was making a decision about surgery. I remember being so opposed to and incensed by reconstruction, and then that changed – and yet the blog doesn’t even begin to express how strong my feelings were. In so many ways, in my memory of that time, I was over-amplifying my outrage in order to compensate for my true desire to reconstruct.

    Today was a bit of a landmark day – well maybe not landmark but important. Over the last few months, I have been showing a little of my naked body in the gym change room. Not usually a lot, but really, I was becoming less and less worried about putting moisturizer on my scars before putting my clothes on. In early days, I would only do this in the shower stall, where I knew I had complete privacy. Today, I chose not to worry in any way. I let my towel drop to my feet, and slowly applied moisturizer before putting clothes on. I just didn’t care anymore. I felt like I was even challenging others to ask the question. If anyone stared, it would be a great conversation starter. If someone asked about my scars or my surgery, I could explain, no this was not a cosmetic choice, rather it was cancer that forced my hand. I was OK with it before, but today, I was just a little more brash about it. I just didn’t care what other people thought.

    I actually seem to have much less of a concern about what the future may hold. If things don’t go well with our green card application, and we end up moving back to Canada sooner than planned, I’m much less worried about it. I used to worry about having to let go of my doctors – not that I’d want to – but now, I know that I’d be ok with going with the flow. Sure I wouldn’t be happy about it – I don’t want any external factors forcing my decisions, but I also know that I’d manage to do OK regardless of the circumstances.

    Today, I’m 3 years older than when I was diagnosed. I’m looking forward to celebrating many more birthdays. Who knows where (or who) I’ll be at this time next year!

  • Memories of illness

    As I delve into my research, I am reading through my cancer blog (http://bcbecky.com) from the beginning. It occurred to me that although I wrote the blog, I had never actually read it. One of the things that jumps out at me as I read is how my memories of things don’t necessarily align with how I blogged about them. Since I intentionally blogged a lot of what I was thinking at the time, I have to take that as my “truth” in that moment – so it is interesting to see how my reflection on what happen are different.

    One particular area of difference is with timelines. I’m finding (and I’ve only read through the first three months) that my memories of how long things took is off. I’m particular off of timelines within the first few weeks. For example, I thought it took us a few weeks before I went to my first support group meeting – this actually happened June 22. It seems that things that I thought took months, actually took weeks, and some things it was only days.

    I’m also struct by early reflections of how my actions and thinking related to one another. I was surprised to learn that my reflection on selfies happened so early on – June 23, 2014 to be precise. I had not even started chemo at that point. I’m not even sure that I had a solid treatment plan yet. So, it is interesting that I was doing so much self-reflection, actually I talk about how breast cancer spurred on deep reflection my second day of blogging.

    I also find myself cringing sometimes at my early thoughts, but also at some of the “facts” that I shared, which I have since learned are not necessarily True. They were my “truth” at the time, that is, I believed them to be true when I wrote them.

    I am intrigued and will report more as I continue to systematically read through my blog.

    Feature image (c) Rebecca J. Hogue


  • In a post-truth world…

    In a post-truth world, I find it rather ironic that I’m studying the lack of a single narrative relating to the patient experience of breast cancer.

    We think of science has having a single truth – big t Truth. The laws of the universe behave in a particular way. However, the human body is complex and each is unique. Each person experiences the world in a different way. We each have our own sense of truth – that is little t truth. It is that little t truth that I’m studying.

    My research looks at my experience with breast cancer treatment. A lot of people don’t realize that the science around breast cancer treatment doesn’t result in a single treatment option. There are choices at almost every stage of treatment. The doctors don’t know what will work and what wont. If you speak to multiple doctors you often get conflicting answers. This makes the patient experience that much more challenging. Add to it that each phase of treatment is handled by a different doctor (breast surgeon, plastic surgeon, medical oncologist, radiation oncology – and that doesn’t include the doctors that treat side effects of treatment – sleep doctor, dermatologist, endocrinologist, physiatrist, psychologist, primary care … the list doesn’t seem to ever end).

    My point is the entire process is complex. There is no single answer to the question. There is no single experience. There is no Truth in this study. There is only my experience, and my view. Sharing my experience and my view helps other patients who are going through similar experiences. Their experiences won’t be the same as mine, but there will be some commonalities. They will need to make some of the same decisions. Their choices may be different, but the things they need to decide are the same. So my experience, and my articulation of how I came to my decisions can be a valuable to others.

    The other point of value, I believe, is in the sharing of how I coped with various mental and physical side effects of treatment. Some of these insights and coping strategies may be of use to others.

    And so, it is interesting that in a world where Truth is being questioned as if it were truth, I’m studying truth not Truth

    Feature image (c) Rebecca J. Hogue

  • Oppression, doctors, and immigration inspections

    As I mentioned in my previous post, I’m reading Freire’s Pedagogy of the Oppressed. So far, I’ve only managed the first chapter (as well as all the front matter). The first chapter has been a bit of a challenge – but I did find that after a while the ideas and concepts were repeating themselves, with slightly different nuances. I am finding that as I read, I compare to the US election, the US anti-immigration/anti-refugee/anti-muslim rhetoric, as well as my context as a patient (which doesn’t’ really compare from a hate perspective, but the themes of objectification still happen – patients become their diseases).

    “It is only the oppressed who, freeing themselves, can free their oppressors” (Freire, 2000, p. 56)

    “the former oppressors do not feel liberated. On the contrary, they genuinely consider themselves to be oppressed” (Freire, 2000, p.57)

    “certain members of the oppressor class join the oppressed in their struggle for liberation…they cease to be exploiters or indifferent spectators or simply the heirs of exploitation and move to the side of the exploited, they almost always bring with them the marks of their origin: their prejudices and their deformations, which include a lack of confidence in the people’s ability to think, to want, and to know” (Freire, 2000, p.60)

    My key take aways:

    • Oppressors dehumanize people and think of them as “things” rather than human beings.
    • The oppressed need to be the ones who break the cycle
    • The oppressors, when things are equal, feel as if they are oppressed
    • The oppressors struggle with feeling that the oppressed are competent

    One of the reflections I had while reading was questioning why I feel uncomfortable with the idea of even asking my care providers (physicians specifically) permission to use their real names / identities in my research. I struggle with even asking them if they want to be a more active “part” of my research, proofreading my interpretations of events and perhaps clarifying their own intentions in the process. A friend mentioned that she was collaborating on research with her surgeon – and I found that to be a very uncomfortable idea. I find that I worry that asking for collaboration puts me at risk of losing healthcare – of being fired by my doctors – and that is definitely a sign of oppressor/oppressed relationship. The funny thing is that I have no issue asking any of the nurses or other allied health professionals (e.g. physical therapists).

    I find that when it comes to healthcare, I’m putting the doctors on a pedestal, and reinforcing the power relationships. This might just give me the courage I need to ask the question – in the non-clinical context.   The care providers that play an active role in my story are almost all clinical professors and a such also have non-clinical email addresses. I find that I think of myself, a PhD Candidate, as somehow inferior to the MDs who are providing my healthcare. The reality is that they have a different set of expertise. I have my own expertise, and it is just as valuable as their expertise. Only, I really do have to submit my life to their hands when it comes to my care (especially the case with surgeons). What is especially odd here, is that I have in some ways collaborated with their research, providing blood samples for their experiments, but also providing pictures of my body, which they used in publication about the type of surgery I had. So I felt OK helping them in their research, and yet I feel uncomfortable asking them to help in mine.

    An Aside: Another book that I finished reading on this trip is: Spare Parts: Four Undocumented Teenagers, One Ugly Robot, and the Battle for the American Dream by Joshua Davis. It is the true story of a robotics team from an impoverished school district in Phoenix Arizona. The setting was rather appropriate for where we are now – as I sit writing this post from the Arizona dessert just south of Why Arizona – where there are signs indicating that human smuggling is illegal. Anyway, this book does a really good job of humanizing the children of illegal Mexican immigrants. The children go to the same schools, and are raised as American rather than Mexican. And yet, if they want to become “legal” they need to go back to Mexico – a place that their parents fled when they were very young – so they have no context of Mexico, nor anyplace to live or call home there. If found that as I read the book, I understood better the rhetoric of what is happening here. Anyways, I really wanted to share the book, as it is very well written and a great story. As we drove past an immigration checkpoint (well within the borders of Arizona), we reflected on how we didn’t have any ID beyond our California drivers licenses. However, we also reflected that we are white, and as result, it isn’t going to be an issue. That is a sad truth.

    Back to the healthcare question – would you feel comfortable asking your doctors to participate in your research? Why or why not?

  • Oppression?

    Maha Bali’s latest blog post on Unpacking terms around equity, power and privilege has got me thinking (actually, I was thinking about it just yesterday, but her post has prompted me to write more about it!). I’m slowly making my way through Freire’s Pedagogy of the Oppressed.

    “But their perception of themselves as oppressed is impaired by their submission in the reality of oppression” (p. 45)

    I’m trying to put this all in context to my research – looking at my lived experience as a breast cancer patient. I am struggling with some of the language. Is what patients experience oppression or is it simply a power imbalance – which doesn’t necessarily mean oppression? But then Freire has me asking myself if my perception is impairing my ability to see the reality?

    Is it oppression when the end goal is caregiving rather than profit making? The purpose of the healthcare system is to care for patients, although there is certainly a level of profit making that is at play. In the US, there are a lot of times when your insurance affects your treatment options. Insurance companies seem to be the ones holding the power here, rather than medical professionals. In that essence, it is both the physicians / care providers and the patients who are in the subservient /oppressed role.

    “the oppressed, who have adapted to the structures of domination in which they are immersed, and have become resigned to it, are inhibited from waging the struggle for freedom so long as they feel incapable of running the risks it requires” (p. 47).

    As a patient, there is a risk of me rocking the boat too much. If you complain too loudly in the US system, you run the risk of being fired by your healthcare providers. That being said, if your healthcare providers suck too much, you often have the ability to change providers. If the ACA (Affordable Care Act otherwise known as Obamacare) gets revoked, then there is a huge risk of the patients who are the worse off already, being unable to get insurance. This adds a layer to the disempowerment of patients. In Canada, what I’ve seen in this situation, is that the patient just loses access to care completely. If you complain loudly enough, doctors stop seeing you – and you don’t always have options (especially if you are located in a rural setting).

    Another place where I personally see struggle is around wait times. In the US, I am privileged to have good insurance. This means that I have easy access to healthcare. In many cases, the wait times are short. I’ve come to the expectation that I get responses from my care team within 48-hours of sending in an email requires. That type of response is unheard of in Canada (frankly, so is emailing care providers!). If I need to wait a couple months for a procedure or specialist appointment, I find myself complaining – but the reality it, my privilege in the US means that I have access that far exceeds what I’d get in Canada.

    Canada has a much more equitable system, but it suffers from huge wait times. In Canada, the only privilege I carry is that I’m educated enough to ask questions. I’m able to figure out aspects of the system that others cannot, and yet I’m still placed in the queue just like everyone else. My privilege does not buy my way to the front of the line, but it does give me the information I need to ask the necessary questions to ensure that I’m waiting in the shortest line.

    And so, I’m in the position of having adapted to the structures of domination, and I know a fair bit about how to play the games I need to play to get things done. With that, I’m hesitant to want to rock the boat, for fear that it would impact my personal healthcare.


    “Any situation in which ‘A’ objectively exploits ‘B’ or hinders his or her pursuit of self-affirmation as a responsible person is one of oppression” (p. 55)

    So this goes right back to my original question. When I’m looking at the patient experience within the healthcare systems, is that one of oppression? The system is intended do provide care, not exploitation. There are definitely power imbalances within the system, but does a power imbalance mean oppression? What do you think?

  • Patient Health Literacies

    In Arthur Frank’s (1995) seminal book The Wounded Storyteller, he cautions “On rare occasions when I have taught this book, students’ biggest initial difficulty is to stop reframing everything ill people say into a question of how some health-care worker might respond.” (Location 115)

    I often find myself falling into that trap. I find myself thinking about my research, and the focus on peer-to-peer patient learning, and yet seem to feel that the value in the research is in the change in how health-care workers respond. Really, my focus should be a change in how my work can help patients and caregivers find agency within the healthcare system.

    This idea of value of knowledge (or value of literacy) is something that Brian Street talks about in Social Literacies: The Schooling of literacy. I talked a little about it in my post on critical digital health literacy. In the chapter I’m reading now, Street (1995) talks about how the definition of what literacy is (the value proposition) is defined by the dominant culture. When we talk of a critical literacy, we are turning that around and looking at it from the perspective of the non-dominant – perhaps those who are seen as not literate.

    In the health literacy context, we see the definition of digital health literacy from the perspective of healthcare systems –  “the ability to seek, find, understand, and appraise health information from electronic sources and apply the knowledge gained to addressing or solving a health problem” (Norman & Skinner, 2008, para. 6). To me, this definition feels like what health professional want patients to have, not what patients necessarily want or need. The health literacy definition is from the perspective of the dominant culture. It is also very solution oriented – as if there were only one solution to the “health problem”. The human body is complex. It is a complex system. There are many different ways in which to approach a health problem, and not all of those involve solutions.

    Now if I look at it from my perspective as a patient, and not a healthcare professional, I can see literacies in a different light. If I look at what I consider important to be “health literate” from a patient perspective, I’d say:

    1. Understanding the disease well enough to explain it to both non-medical professionals and medical professionals (knowing that the language of the medical profession is not the same as the language used by the general population).
    2. Understanding the healthcare system well enough to get the care you are looking for. This in part means knowing who to ask which questions to, and knowing even what things are available to you as a patient. Understanding the hierarchies within the healthcare system helps to ensure you are asking the right people the right questions.
    3. Knowing where to go to get support from peers.
    4. Knowing how to identify individual experiences of disease experience versus generalized experiences. That is, developing an understanding of what aspects are typical and what aspects are unique to the individual experiencing the disease.
    5. Understanding the disease well enough to search for information on the internet, and discern appropriate sources of information (e.g. being able to identify snail oil).

    My question to you is, as a patient, what you see as the important things YOU need to know in order to manage your personal health? 

    Feature image: By NASA/MSFC/David Higginbotham – NASA Image of the Day, Public Domain, Link

  • Primary versus secondary use of blog data in research

    I’ve previously talked about researchers using blogs as data sources in their research. I have argued that since blogs are self-publication, then bloggers should be cited appropriately in research reports.

    When data is collected specifically for research purposes, we talk about primary data collection. When data is collected for a different purpose, but then later used for research purposes, we call that secondary use of data. Secondary use of data generally requires approval from research ethics boards to ensure that the data was originally collected in an ethical manner, and that the secondary use of data does not put research participants in any form of harm.

    The rules of engagement around blogging stem from whether or not the blog text is seen as a publication that is publicly available. Further, when it is seen as its own genre, then can a blog be used as a publication would or does it become a data source that would require secondary use of data approval? If the blog is a data source that is used by researchers, the data can be seen as having been generated for a different purpose, and as such, the researcher should then be required to seek secondary use of data approval. In most cases, this then requires that the researcher get permission from the data owner (in this case the blogger) for use of the blog data within their research study.

    In addition, I’ve seen research that confuses the blogger with a research participant, or in the case of health blogs, as a patient. In the case where the researcher is using public blog data without interaction with the blogger, then the blogger should be considered neither a research participant, nor a patient. The blogger, in this case, is a published author. The blog, is a publication, and should be cited appropriately in research reports.

    So, should the use of ‘blogs as data’ for research purposes require secondary use of data approval?


  • Critical Digital Health Literacy

    Digital Literacy – Read, Write, Participate (e.g. https://learning.mozilla.org/en-US/web-literacy)

    Digital Health Literacy – “the ability to seek, find, understand, and appraise health information from electronic sources and apply the knowledge gained to addressing or solving a health problem” (Norman & Skinner, 2008, para. 6).

    Critical Digital Health Literacy – the ability to seek, find, understand, and appraise health information from electronic sources to not only apply the knowledge gained addressing or solving a health problem, but also to participate in the healthcare system.

    Aligning with the discussion I just finished on Open Dissertations, I have decided to share a half-baked (draft) idea with you. One might say that this blog post belongs in the land of not-yetness :-).  I welcome discussion and feedback – and reference for articles/books I should read. I use the term healthcare provider to mean any healthcare professional, including doctors, nurses, therapists, etc.

    Digital health literacy has been defined as “the ability to seek, find, understand, and appraise health information from electronic sources and apply the knowledge gained to addressing or solving a health problem” (Norman & Skinner, 2008, para. 6). I want to explore this further, as I feel that the definition is not complete. It touches on the technical aspects of digital health literacy, but misses the contextual issues and social issues associated with developing a new literacy. It also doesn’t address patients’ participation in the generation and dissemination of health related knowledge.

    “The questions that have mostly been asked by agencies attempting to introduce literacy to societies where it is not been widespread, have generally stemmed from emphasis on the technical problems of acquisition and how these can be overcome.” (Street, 1995, p.28).

    “By definition, literacy is being transferred from a different culture, so that those receiving it will be more conscious of the nature and power of that culture then of the near technical aspects of reading and writing.” (Street, 1995, p.30)

    Street’s (1995) description highlights a challenge in Norman & Skinner’s (2008) definition of digital health literacy, as the focus is on the technical acquisition of knowledge as is defined by health professionals. However, those that are receiving this health information are not from the dominant culture – where the dominant culture can be seen as the language of healthcare professionals. So, the problem of digital health literacy from a patient perspective is in the application of health information into the specific context of that patient, where the context includes medical condition but also the country and the culture of the patient and healthcare provider.

    “In many situations it is the dominant group within a society that is responsible for spreading literacy to other members of the society into subcultures within it” (Street, 1995, p.30)

    We see this in healthcare education. It is healthcare professionals (dominant group) who are responsible for educating the patients. Street (1995) highlights that literacy is not just a learning of new skills but also involves “profound changes in people sense of identity and then what they took to be the basis of knowledge” (p.31). In the context of critical health literacy, the patient identity and role shift from a passive patient who follows doctors orders, to a patient who works with their healthcare team to come up with treatment plans that work for that individual patient. Health literacy involves a shift in power, but not a total shift, from healthcare provider to patient, allowing the patient to take some control over their healthcare.

    When it comes to digital sources, the definition of what is considered useful or valid is from the perspective of the dominant group – the healthcare provider. However, many patients also value information that comes directly from other patients, rather than information that is pushed down from healthcare providers. Patients are the experts in their own lived experience, however, lived experience information is not valued by many healthcare professions unless the patient is also a healthcare professional. For example, when a medical doctor who gets cancer then blogs about their patient experience with cancer, their blog is seen with a much higher regard than a blog by someone who is not a healthcare professional. However, that doctor doesn’t experience the patient role the same way patients who are not doctors experience the patient role. Again, we have someone who is in the dominant culture being given more credibility and yet their experience is not representative of the experience for those who are not in the dominant group.

    I feel like what I’m trying to do here is to provide validation for the sharing of patient voices in the language that patients understand. The goal is not upward communication, that is, the goal is not to allow patients to better communicate with their healthcare providers, rather the goal is to help patients better understand their experience using language that they understand. We see in patient blogs the adoption of medical terminology. Patient bloggers do not make up a completely new language, rather, the language use is a mixing of the medical terminology with the non-medical language that is used by everyday people. So the focus is on peer-to-peer ways of communicating.

    My argument is that one of the goals of critical digital health literacy is about giving voice to patient narratives for the purpose of helping patients better understand their lived experiences. I say one of the goals because I agree that a goal is to improve patient-healthcare provider communication, but I also want to add to it that there is also an aspect of patient-patient communication that is just as important or maybe even more important for those dealing with chronic or critical illness.

    Aligning with the goal of critical theory, there is a social justice cause in critical digital health literacy. This literacy helps to highlight the problems with the traditional methods of medicine where the doctor is see as the expert and the patient is in a subservient role as someone who healthcare is performed on rather than with. In traditional models the patient is a passive receiver of healthcare, rather than someone who takes an active role in their personal healthcare. Part of developing a critical digital health literacy is to help patients gain the knowledge and skills they need to find their own voice within their own healthcare. There is also a goal to help those patients who wish to advocate for change, the knowledge and skills necessary to do that advocacy work.

    On this front, my personal social justice activity was to create a course called Should I blog? (available at shouldiblog.org). When I created it, I had no thoughts of critical digital health literacy or what role the course might play in such thing. Now, I can see that it is a small part of what is needed to help patients find their voices, but also help patients find other patients so that they don’t feel so alone.

    References:

    Norman, C.D., & Skinner, H.A. (2006, June 18). eHealth literacy: Essential skills for consumer health in a networked world. Journal of Medical Internet Research 8(2). Doi: 10.2196/jmir.8.2.e9

    Street, B. V. (1995). Social literacies: Critical approaches to literacy in development, ethnography and education. New York: Longman Publishing.

  • Growing your PLN

    This summer I’ll be teaching a new course on Leadership of Learning in the Digital Age. I’m designing the course as a combination of leadership skills (emotional intelligence) and digital literacy skills. One key aspect of the course will be to have students work on defining and expanding their personal learning network (PLN). In leadership terminology, the idea here is grow your social capital. From my perspective, I see it as growing the network of people who help me to continue learning.

    One bit of advice I received was to make sure that I modeled the behaviors that I’m teaching. One example of that modeling is this blog, and my personal internet presence. This idea then made me start to conscious think about the things that I do (and have done) to help grow my personal learning network. How do I keep it alive and continue to feed it.

    Currently the one of the most important things I do for my online network is Virtually Connecting (VC). VC has done so much for expanding my personal learning network. I love that I have so many new colleagues and even new friends as a result of what I do at Virtually Connecting. I’m working now at expanding that space into the Engaged Patient (ePatient) space. The transition is not an easy one, but it has been a valuable one for my learning. I also love seeing how Virtually Connecting is helping others.

    Another thing I do is to reach out to people and ask about their research, or ask for a copy of their paper. I use Google Scholar Alerts to find the latest research papers on topics that interest me. When something that comes up that looks interesting but isn’t available through my university library (which is often the case with alerts about papers that haven’t been published yet), I try to see if I can find an email for the author (or if they are on ResearchGate or Academia.edu). If I can find a way to communicate directly with the author, I send them a message introducing myself and asking them a question and for a copy of the paper. This gives me an opportunity to reach out and have a dialogue with scholars who are doing work that I find interesting. It sometimes leads to further conversations. It is also very rewarding when someone answers your email.

    Earlier in my academic career I participated in Connectivist MOOCs. These MOOCs gave me ideas for blog posts, but also gave me a chance to connect with others. Participating in the blogosphere, and linking to other people’s blogs, has done a lot for my PLN.

    Now I think back to something that Michael Berman said to my class, networking is 80% giving and 20% getting. I am now thinking about what I do to give back. Early in my academic career, I monitored #phdchat on Twitter. If I could, I’d answer people’s questions. I also think that blogging helps other people learn. I connect other people’s ideas with what I’m thinking, and that helps both of us. Recently, I’ve done most of my work in mentoring breast cancer patients. It is hugely rewarding to know that I can help someone making their experience just a little less sucky (cause cancer sucks). While I was in treatment, I developed the Should I Blog (http://shouldiblog.org) course. It is something that I hope to update and launch again sometime in the next few years – but right now my time is going towards finishing my PhD and teaching.

    I’m sure there is more. My husband says that I sell myself short when I think that I’m not going at networking or to use dry business leadership terminology – building social capital.

    What do you to build and continually improve your personal learning network? Any tips for my future students who may have very little internet presence at the beginning of the course?

  • Health (Illness) bloggers

    In my literature review for my research I came across a great article (Keating & Rains, 2015) on the social support health (illness) bloggers receive. The article does a good job looking at social support of bloggers over a three year period.

    One of the things that came clear in the article is the use of the term health blog rather than the term illness blog. It has really got me thinking. A lot of bloggers shy away from the term illness blog because of the negative connotation around it. My immediate thought was the opposite of illness blog is wellness blog, but the term wellness blog is already used for those who are promoting wellness (e.g. diets, exercise routines, etc). Although the health (illness) blogs are written by someone who is experiencing illness, the focus of the blog is often the personal journey – and that journey is someone trying to figure out what health looks like for themselves. I do like the more positive connotation that health blog implies.

    I pulled out the following findings from the article:

    “The results indicated that changes in support available from blog readers and from family and friends over the course of 3 years were significant predictors of changes in bloggers’ well-being. Increased support availability from bloggers’ family and friends was associated with a decrease in bloggers’ feelings of loneliness and an increase in their feelings of health self-efficacy” (Keating & Rains, 2015, p.1454)

    The article makes mention of the idea of strong-ties and weak-ties. Strong-ties would be those with close family and friends. These are the people you can call anytime. They are your primary support. Weak-ties are those of acquaintances. They are not necessarily your close friends, but they still provide support through your experience. In this case, bloggers often have weak-ties with other bloggers. These weak-ties also help in increasing the feeling of support and decrease feelings of loneliness. I think we need both.

    “The results also demonstrate the benefits of blog reader support and suggest that this type of support can serve as a unique resource about and beyond strong ties. After we controlled for changes in support available from family and friends, change in blog reader support was associated with decreased health-related uncertainty. Bloggers who reported an increase in support from blog readers across the two measurement periods also felt that their health condition was less unpredictable” (Keating & Rains, 2015, p. 1454)

    What really resonated with me here is the idea that reading blogs helped to make my experience with breast cancer treatment less unpredictable. I was able to read a lot about people who had experienced the same surgery and breast reconstruction – so I better understood what my experience might be like. You cannot fully predict your experience as each journey is individual, but it really does help to have some general ideas of what you might experience as well as some tips on how to better cope.

    “In addition, the findings suggested that bloggers who perceived themselves as being in better health at the first time point were less likely to continue blogging over an extended period of time. It could be the case that those who evaluated themselves as being in better health were less likely to perceive value in continuing to document their experiences” (Keating & Rains, 2015, p. 1455)

    The idea that we blog less when we are healthy is something that I’ve definitely seen and experienced. We often feel like when things are going right we have nothing to say. A blog post that says “today was normal” does not feel that interesting, and yet, it is an important thing to say. It is really important to celebrate the good days, so that the blog is also providing encouragement to other patients. When cancer bloggers stop blogging we assume one of two things (1) they are healthy and don’t think they have anything interesting to say, or (2) they have died.

    “Through connecting authors with individuals who are coping or have coped with a similar condition, blogs appear to be a particularly useful resource for helping individuals to better understand their illness experiences” (Keating & Rains, 2015, p.1455)

    As a blogger, and one who reads blogs, I completely agree. Reading other blogs did help me better understand my experience. Overall, I did find that this particular study aligned with my experience as someone who both authored and followed breast cancer blogs. Now I just need to get into the habit of using the term health blogger rather than illness blogger.

    Reference

    Keating, D. M., & Rains, S. A. (2015). Health Blogging and Social Support: A 3-Year Panel Study. Journal of Health Communication, 20(12), 1449-1457. doi:10.1080/10810730.2015.1033119

  • Illness blogs as a data source for health sciences research – #ethics

    This post is a follow up on my post The ethical use of twitter and blogs in research as well as the series of blogs posts on the ways in which breast cancer blogs are being used in research. Today I want to talk about a specific example of what I see as a problematic use of illness blogs as research data. Blogs are used as data in a variety of fields of study; however, most are not as problematic in their use as those in health related fields of study.

    The particular study that I was looking at this time is:

    Weber, K. M., & Solomon, D. H. (2008). Locating relationship and communication issues among stressors associated with breast cancer. Health Communications, 23(6), 548-559. doi:10.1080/10410230802465233

    The first red flag in the article appeared early on when it talked about the ethics approval for the study itself. The authors state:

    “After we received institutional review board approval, we collected accounts from various breast cancer message boards, weblogs, and chat rooms, and we conducted a theme analysis focused on the sources of distress voiced by contributors” (Weber & Solomon, 2008, p. 550).

    It may be related to the age of the article, but today, a lot of the social media sites (e.g. message boards and chat rooms) explicitly state that the information provided is not to be used for research purposes. The act of “collecting accounts” means that the information collected was not necessarily available to the public. As such, the participants in the message boards and chat rooms specifically, had an expectation of some level of privacy. If the researchers did not seek explicit permission to use the conversations, they were unethical in the manner in which they collected the data. Of course, I can see this through the lens of social media in 2017. It is hard to think of what the researcher lens would have been in 2006/7 when they were conducting the study.

    The next problematic area is:

    “Quotes in the pages that follow use pseudonyms to maintain the anonymity of contributors, per institutional review board protocol … all quoted material is reproduced exactly as written, and grammatical and spelling errors were not corrected” (Weber & Solomon, 2008, p. 551).

    In this requirement for pseudonyms and anonymity, the institutional review board has required that the researchers cite their data in a way that is inconsistent with current guidelines. It is with blogs that I see the biggest problem. Bloggers have chosen to share their stories in a self-published public format. Not attributing their words most likely does not align with the desire of the blogger. If the text had been composed into a book format, i.e. a pathography, then then researcher would have a clear method for citing the quotation. Since the text is a blog, the ethics boards seems to be confusing the ideas of participant privacy with public citations.

    I recall being told that the rule of thumb for anonymity of participants is that the participant should not be able to be identified using basic journalistic tools. In the case of internet sources, this means that I shouldn’t be able to identify the anonymized participant through a simple search. I tried this with a few of the quotes in the paper. This one specifically:

    “The ultrasound technician’s face told me it wasn’t routine… I waited a tense hour, then came back to pick up the screens and report. I walked back to my car, willing myself not to open it, to give myself another five minutes where I didn’t know. (24)” (from Weber & Solomon, 2008, p.553 – however, the actual source is a blog post written by Alunta Thornton on Tuesday June 8, 2004).

    I want to highlight that bloggers have chosen to share their stories in public spaces. Blogs are publications. When you use a public data source for your research, you are expected to cite it appropriately. But for some reason, the health sciences fields specifically, feel the need to take away the identifying information. My belief is that research ethics boards (REB or IRB) in the health related fields have a heightened concern for research participant anonymity, and with that they have lost sight of public versus private data.

    I read this article with mixed emotions. I found myself asking whether or not the research project itself was done in an ethical manner? And if it is not done in an ethical manner, then should I dismiss the findings? Should I be careful not to reference it?

    The other question I find myself asking is, at what point in time should blogs be considered self-publications, rather than data on the internet? If it is 10 years old, does that mean it is OK that the researchers and research ethics boards didn’t understand how blogs should be used ethically in research? Is it just a matter of a lack of familiarity with the media? And frankly, in 2017, why am I still running into this issue? Why do health science / medical ethics boards today have so much trouble with allowing people to chose to NOT be anonymous in research?

    Feature image by Randall Munroe (en:User:Xkcd) – http://xkcd.com/285/, CC BY 2.5, Link

  • Tagging my posts

    One of the first steps (I don’t have a linear process so there isn’t really one first step) in my research is to tag all my blog posts. I didn’t really use the tagging feature when I wrote the original posts. So now, I’m re-reading and tagging highlighting which posts provide insight into my experience with health literacy – but also key things within my story. I’m also cleaning up the post categories.

    I’m not cleaning up the text itself. I’m leaving in all the typos and errors. It is difficult to leave the early posts this way – the later posts have a lot few typos as I gave my husband edit access at some point and he fixed them.

    I don’t want to change the post content in any way, as that would be corrupting the data that I’m using for my research. I also think it wouldn’t be a reflection of what I was feeling at the time. The blog gives me insight into my thought processes back then. It is interesting to see how I repeated myself across posts, in part because I didn’t remember what I had already written. There are memories that I had forgotten about. Nightmares that I only now vaguely remember having read the blog post.

    What I also can feel as I read the posts is the emotions I was going through at the time. I carried a lot of fear. I carried that fear for a long time. I can see it my posts. I can feel it as I read through it, but only in a soft way. A lot of the fears I had back then don’t carry the same weight with me now. I’ve come to terms with what I’m facing, and I understand it a lot better. I am not living every day with a blanket of fear.

    And so with that cheery thought – I’m going to go do some reading of literature and perhaps dive some more into dissertation work, because any other news today is too darn depressing to watch.

  • Shifting my research question

    In the spirit of open dissertations, I figured I’d write a little more about where I’m headed with my dissertation. My last two weeks were spent up in Ottawa for the Association for Interdisciplinary Studies annual conference and a committee meeting followed by the Open Ed conference in Richmond Virginia. I have to say my head is still spinning for all that I got out of both conferences and my committee meeting.

    For some background on the ideas behind open dissertations see Laura Goglia’s blog post Granularities of the Open Dissertation and Bonnie Stewarts blog post Opening the dissertation: Why we need to make open the default. They both presented at Open Ed, but unfortunately, I missed their presentation.

    The idea of open dissertations isn’t new to me. The bigger question to me is what parts of the dissertation are open in an open dissertation? I am finding that the open part of the dissertation has mostly been the last part – the part after the committee has approved everything. It is like using open to get a sneak peek into what will be open in 3-6 months.

    My challenge with open is that my research process doesn’t follow the standard linear progression of a research topic. The lit review, proposal, ethics, data collection, data analysis, write up findings process doesn’t align with the way in which I’m doing my research. I seem to be doing all the parts of the process at the same time. Of course this makes it that much more challenging, as it is unclear when ethics is required and for what ethics is required. But that is a discussion for a different blog post (actually something that I have reflected upon previous).

    My primary source of data is already open – my breast cancer blog being my primary data source. I am writing about my experience. The current iteration of my research question is “What was my lived experience with breast cancer?” I’m rewriting blog posts in the style of evocative autoethnography described by Bochner and Ellis in the book Evocative autoethnography: Writing lives and telling stories. I’m also looking at My experience with developing health literacy and advocacy.

    The open dissertation discussion doesn’t really talk about the process of doing the earlier parts of the dissertation in the open. Since my primary data is already open, there are a bunch of ethical questions on how to go about doing my research. For example, in my research I’m encouraged to not name the organizations that provide my healthcare, in part because it would be somewhat easy to identify my surgeon based upon my story. However, I’ve identified the organizations in my blog. I’m not about to go back and change my blog entries to remove those names. And given where I live, which is an important part of the story, it is pretty obvious what those organizations are anyways.

    I feel like I’m grappling with so many different things around my research project that I need to blog about it. But I also find myself holding back. I find myself writing snippets and then asking myself, How much can I share now? How open can I be? What will I jeopardize by blogging about my experience of this process?

    I’m also finding myself wondering if anyone in Canada does autoethnography and how they approach research ethics boards? There is a lot written in the US, but most US research ethics boards call autoethnography memoir (creative works) and exempt it from requiring ethics approval. That is not going to happen in my school. And so, I’m needing to negotiate the ethics approval process while I work on actually writing my story, reading the literature (which never ends because there are so many different angles to my story), and writing the analysis of the story. In writing the story, I grapple with various ethical considerations around representation of others in my story, but also on how I tell my story, what I leave out, and what I include. There are so many different decision points.

    Part of me thinks that things would be a lot easier if I just gave up on the PhD and got down to writing the story – however, it is the act of doing the PhD that is helping me write a much better story. It is the act of going through the literature and linking my story to different themes that is making my writing so much better.

    And with that, I’m hoping to see more and more PhD students opening up the dissertation process – and not just the final results. I feel like challenges to opening up the process can only happen one dissertation at a time!

    Feature image CC0 public domain via Pixabay

css.php

